jhc-2019-jul-v-3-n-2-analysis-ray-s

Analysis of the Diagnostic Value of Cytological Smear Method Versus Cell Block Method in Pleural Effusion Fluid of Suspected Lung Cancer Patients

 *Ray S,1 Zinnah SA,2 Awal N,3 Hassan I,4 Dewan RK,5 Jeba R,6 Hussain M7

 *Dr. Subrata Ray, Assistant Professor, Department of Pathology, Jashore Medical College. subrataray29@gmail.com

  1. Shahed Ali Zinnah, Associate Professor, Department of Pathology, Dhaka Medical College.
  2. Dr . Naila Awal , Assistant Professor, Department of Pathology, Greenlife Medical College.
  3. Imran Hassan, Assistant Professor(CC), Department of Pathology, (Col) Malek Medical College, Manikgonj.
  4. Rezaul Karim Dewan, Professor and Head, Department of Pathology, Dhaka Medical College
  5. Dr . Ruksana Jeba, Associate Professor, Department of Pathology, Dhaka Medical College.
  6. Dr Maleeha Hussain, Professor, OSD, DGHS.

 *For correspondence

 Abstract

Background: For any kind of lungs pathology accompanying pleural effusion pleural biopsy guided with thoracoscopy, of course, may provide important results. Since biopsy is an invasive procedure, the priority is to do,  a cytological examination of pleural fluid obtained with thoracentesis, which  is very crucial for the disease staging and treatment strategy. In this purpose, even though conventional cytosmear techniques have been used generally till this day, cell block technique is also being used recently.
Methods: In our study, 100 pleural effusion fluid sample were included. All the fluid specimen was subjected to cytosmear (CS) and cytoblock (CB).
Results: By using conventional CS method, 85 fluid specimens were diagnosed as negative for malignancy (85%), 5 cases were diagnosed as positive for malignancy (5%) and the remaining 10 cases were diagnosed as suspicious for malignancy (10%). On the contrary by using CB, complimented by combined PAS-Alcian blue stain where required, 90 cases were diagnosed as negative for malignancy (90%) and 10 cases were diagnosed as positive for malignancy. Thus, by the CB method, an additional 5 more cases were diagnosed as positive for malignancy, that is, 5% more diagnostic yield for malignancy.
 Conclusion: CB technique could be considered as a useful adjunct in evaluating malignant cells in MPE for a final cytodiagnosis, along with the routine CS method.

[Journal of Histopathology and Cytopathology, 2019 Jul; 3 (2):99-106]

 Key Wards: Cell block , Pleural effusion , Lung cancer 

Introduction

Development of pleural effusion is a common complication in patients with lung cancer either primary or secondary. There may be presence of neoplastic cells in the pleural effusion which is called malignant effusion (MPE) or it may be a para-malignant effusion, which is  pleural effusion with absence of cytological evidence of tumor cells in a known setting of malignancy. In UK, 40000 people per year are affected by MPE and it is estimated that up to 50% of the patients  with metastatic malignancy  develop a pleural effusion – either at the time of diagnosis or during the evaluation of cancer.1,2,3  The common etiologies of MPE are lung cancer, breast cancer, lymphoma, ovarian cancer and gastric cancer in order of decreasing percentage.

For any kind of lung lesion accompanying pleural effusion, pleural biopsy guided with thoracoscopy, of course, may provide important results, but has the risk of being an invasive procedure and it depends on the experience and efficiency of the surgeon. So, in a country with poor resource settings, the priority should be a cytologic examination of pleural fluid obtained by thoracentesis. It not only helps in diagnosis but also can help in disease staging and treatment strategy.4

In conventional cytological smear (CS), discrimination of the reactive mesothelial cells and malignant cells is the most important diagnostic problem. Distinguishing benign from malignant cellular changes may require meticulous screening, careful scrutiny of cellular features and an understanding of the range of reactive changes. Since the introduction of cell block (CB) technique by Bahernburg nearly a century ago,  it has been used routinely for processing fluid.5 CB has the advantage of recognition of the histological pattern of disease, possibility of study multiple sections by routine staining, special staining and immunological procedures.

In this study, we assessed the utility of CB and CS techniques and evaluated whether the CB, when it complements conventional CS, can increase the diagnostic yield.

Methods

This is an analytic study, carried out at the Department of Pathology, Dhaka Medical College, Dhaka from  July 2015 to  June 2017, over 100 pleural effusion fluid specimen of suspected lung cancer patients.

 10 ml of fresh pleural fluid sample was obtained by thoracentesis from each patient during clinical evaluation. Each sample was divided into two equal parts.

For conventional smear technique, 5 ml fluid specimen was centrifuged at 2500 rmp for 10 min. A minimum two smears were prepared from the sediment. They were immediately fixed in 95% alcohol and stained with the Papanicoloau and Haematoxylin- Eosin stain.


For cell block, we used AAF (95% ethyl alcohol + acetic acid + 10% formalin). After centrifuge at 2500 rmp for 10 min, cell sediments were mixed with thrice the volume of AAF fixative and again centrifuged at 2000 rmp for 10 min. The centrifuged tube was aside undisturbed for six hours. The cell button was scraped out and wrapped in filter paper and processed in automatic tissue processor for routine histopathological sections. The cell blocks were embedded in paraffin and sectioned at 4 micro meter thickness.

 The samples were studied in detail taking into account the available clinical and radiological data and various investigation reports. Each individual slide was objectively analyzed for cellularity, background blood, nuclear and cytoplasmic details and arrangement of the cells using the point scoring system described by Mair et al., (1989).6 All these criteria were put together and each cases was categorized as Benign, Suspicious for malignancy and Malignant effusion. Special stain of cell blocks, including combined PAS-Alcian blue stain was done whenever needed. In cases, where pleural biopsy of the same patients was available, used to confirm the diagnosis.

Results

In our study, 100 pleural effusion fluid sample were included. The age-rang from 26 to 82 years. Most of the patients are between the age group 51-60 years (30%). The male female ratio was 1.8:1. All the fluid specimen was subjected to CS and CB. By using connectional CS method, 85 fluid specimens were diagnosed as negative for malignancy (85%), 5 causes were diagnosed as positive for malignancy (5%) and the remaining 10 causes were diagnosed as suspicious for malignancy (10%).On the contrary by using CB, complimented by combined PAS-Alcian blue stain where required , 90 cases were diagnosed as negative for malignancy (90%) and 10 cases were diagnosed as positive for malignancy. Thus by the CB method, an additional 5 more cases were diagnosed as positive for malignancy, that is, 5% more diagnostic yield for malignancy .

Among the 10 malignant cases, diagnosed by CB, 9 cases were subcategorized as adeno carcinoma (90%) and 1 cases was diagnosed as lymphoma.

The malignant effusion was more common in male (70%) than female (30%). The male female ratio was 7:3.

When the cytological smear and cell block techniques were studied for their quality using the point scoring system of Mair et al, (1989).6  it was noticed that 5% of the CS and 6% of the CB was inadequate and unsuitable for diagnosis. 50% of the CB and 32% of the CS showed highest cellularity. 41% of the CB and only 11% of the CS yielded highest morphological details. Wilcoxon Signed Rank test was done to measure the level of significant, which was highly significant in CB compared to CS regarding cellularity and morphological details.
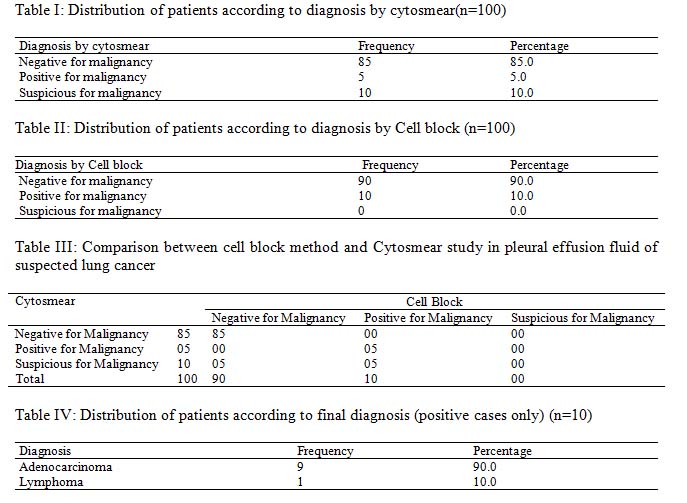

Table V: Distribution of patients according to point scoring system adopted by Mair et al,(1989)6 in CS


Discussion

Lung cancer, whether primary or secondary, is invariably accompanied by pleural effusion. The cell population in sediment of pleural fluid represent much larger surface area than obtained by needle biopsy.  Malignant cells first involve the visceral pleura and tend to be focal in the parietal pleura.7 This explains why, pleural fluid cytology is a more sensitive diagnostic test than closed percutaneous pleural biopsy.8,9

Thoracentesis followed by cytological examination is the first investigation performed in a pleural effusion fluid of a suspected lung cancer patients and has been accepted as a routine laboratory procedure. The differentiation of a malignant effusion from a para-malignant effusion is extremely important, not only in the diagnosis of a malignant lesion, but also in staging, prediction of prognosis and to reform a proper treatment protocol.10

In our study, 100 pleural effusion fluid specimen of radiologically and clinically suspected lung cancer patients were examined by using conventional CS and CB techniques. In CS, of 85 patients, the fluids were diagnosed as negative for malignancy (85%).

All the 85 negative cytosmear cases were confirmed by CB. In conventional CS method 10 cases were diagnosed as suspicious for malignancy, of which 5 cases turned to be negative and another 5 cases   proved to be positive for malignancy in CB. In conventional CS method, reactive mesothelial cells, an abundance of inflammatory cell and paucity of representative cells contributed to the considerable difficulties in making conclusive diagnosis of malignancy.

The false positive diagnosis in CS was secondary to the marked atypia of the mesothelial cell which may be due to the microbiological, chemical, physical, immunological or metabolic insult to the serous membrane or due to the subtle cytomorphological features of some malignant neoplasm, particularly well differentiated adenocarcinoma.11 The problem was compounded by artifact   caused by poor fixation, preparation and staining technique. In our settings, fixation and transportation are contributory factors. Generally the reactive mesothelial cells appears rounded and have single centered or eccentric nucleus. Some of the mesothelial cells form cell ball, clusters and takes a signet-ring cells appearance, thus closely mimicking malignancy. The malignant cells have irregular nuclear membrane, nuclear molding and prominent nucleoli with absence of windows. However, these differentiating features are sometimes difficult to identify.

By using CB method, 5 more malignant cases were diagnosed, which were diagnosed as suspicious for malignancy by conventional CS, thus increasing the diagnostic yield by 5% (5/10). Further special stain (PAS-Alcian blue) supported the diagnosis of malignancy.

Another 5 cases were diagnosed as negative for malignancy by CB, which were diagnosed as suspicious for malignancy by conventional CS. The benign cells did not take PAS-Alcian blue stain.

In a parallel study on effusion fluid, Shivakumaraswamy et al, (2012)5 found   15% more diagnostic yield for malignancy on CB.   Bhanvadia et al., (2014)12 in another study observed    10% more diagnostic yield in CB. Thapar et al, (2009)4  also   showed 13% more diagnostic yield by CB.

In our study, after the final diagnosis as benign or malignant effusion, a critical evaluation was made for diagnostic yield taking a consideration on cellularity, morphology, architecture and background blood. The conventional CS and CB technique were studied for their quality by using point scoring system of Mair et al, (1989).6 In CB, 41% ensured highest morphological details where as in CS, highest morphological detail was acquired in only 11% cases. The comparative result of our point scoring system was analyzed by Wilcoxson Signed Ranks test which was highly significant in respect of cellularity and cellular morphology.

Reactive mesothelial cells have in the past been responsible for simulating malignancy in CS, largely due to the formation of rosettes, pseudo acini or acini, with or without the presence of prominent nucleoli. The CB effectively puts both the features in their proper prospective. That is, the nucleoli does not appear as prominent in CS and the pseudoaciner or acinar strictures can be better appreciated when present in the CB. Similar findings were noticed in the Dekker and Bapp (1978)(13) study. More important is, this CB is a valuable tool in the evaluation of well differentiated adenocarcinoma, where the presence of true acini is seen in the CB with mucin. Positive stain  for mucin in CB  indicated  malignancy.

In our study, we noticed a significant number of macrophages admixed with malignant cells having large pleomorphic nuclei simulating malignant cells. Multiple large PAS positive granules were identified by special stain that were diagnosed as suspicious for malignancy by CS. We also noticed pericellular lacunae in many of the cases of adenocarcinoma specially of mucin secreting type, characterized by cell clusters and Bull’s eye (Target) inclusion like finding was seen in one case of metastatic carcinoma.

There had not been yet any standard method for the preparation of CB from effusion fluid. Our study was done by using 10% alcohol formalin fixative. In our paraffin embedded CB section our attention was drawn by the presence of large clusters of cells either malignant or reactive mesothelial cells in a separate peripheral layer leaving a  thick amorphous proteinaceous material in the center. These helped in reducing background artifact and ensured more nuclear details for the distinction between reactive mesothelial cells and malignant cells. Few inflammatory cells were noticed in a less peripheral separate layers admixed with other cells in malignant cases. The other advantage of CB was concentration of cellular materials in one small area that can be evaluated at a glance with all cells lying in the same focal plane of microscope. It bridges the gap between cytology and histology

Conclusion

The cell block made by using 10% formalin-alcohol as a fixative, is a simple, inexpensive method, and does not require any special training or instrument. Multiple sections could be obtained required, for special stain. Therefore, CB technique could be considered as a useful adjunct in evaluating malignant cells in MPE for a final cytodiagnosis, along with the routine CS method.

References

  1. Kastelik JA. Management of malignant pleural effusion. Lung, 2013;191(2):165-75.
  2. Bennett R & Maskell N. Management of malignant pleural effusions. Curr Opin Pulm Med, 2005;11(4): 296-300.
  3. Maskell N, Gleeson F & Davies R. Standard pleural biopsy versus CT-guided cutting-needle biopsy for diagnosis of malignant disease in pleural effusions: a randomised controlled trial. The Lancet, 2003;361(9366):1326-30.
  4. Thapar M et al. Critical analysis of cell block versus smear examination in effusions. Journal of Cytology, 2009;26(2):60–64.
  5. Shivakumarswamy U, Arakeri SU, Karigowdar MH & Yelikar BR. Diagnostic utility of the cell block method versus the conventional smear study in pleural fluid cytology. Journal of Cytology, 2012;29(1):11–15.
  6. Mair S, Dunbar F, Becker PJ & Plessis WD. Fine needle cytology–is aspiration suction necessary? A study of 100 masses in various sites. Acta Cytologica, 1989;33(6): 809-13.
  7. Rodrîguez-Panadero F, Naranjo FB & Mejîas JL, 1989. Pleural metastatic tumours and effusions. Frequency and pathogenic mechanisms in a post-mortem series. European Respiratory Journal, 1989;2(4):366-9.
  8. Johnston WW. The malignant pleural effusion. A review of cytopathologic diagnoses of 584 specimens from 472 consecutive patients. Cancer, 1985;56(4):905-9.
  9. Prakash UB. & Reiman HM. Comparison of needle biopsy with cytologic analysis for the evaluation of pleural effusion: analysis of 414 cases. Mayo Clinic Proceedings, 1985;60(3):158-64.
  10. Rivera MP, Mehta AC & Wahidi MM. Establishing the diagnosis of lung cancer: Diagnosis and management of lung cancer, 3rd ed: American College of Chest Physicians evidence-based clinical practice guidelines. Chest, 2013;143(5):e142S-e165S.
  11. Price BA, Ehya H & Lee JH, 1992. Significance of pericellular lacunae in cell blocks of effusions. Acta Cytologica, 1992;36(3):333-337.
  12. Bhanvadia VM, Santwani PM & Vachhani JH, 2014. Analysis of Diagnostic Value of Cytological Smear Method Versus Cell Block Method in Body Fluid Cytology: Study of 150 Cases. Ethiopian Journal of Health Science, 2014;24(2):125–131.
  13. Dekker A & Bupp P A, 1978. Cytology of serous effusions. An investigation into the usefulness of cell blocks versus smears. American Journal of Clinical Pathology, 1978;70(6):855-60.
jhc-2019-jul-v-3n-2-The-Incidental-awal

The Incidental Findings of Thyroid Neoplasms in 200 Sequential Autopsies in Dhaka Medical College

 *Awal N,1 Dewan RK,2 Ray S,3 Ferdous JN4

  1. *Dr. Naila Awal, Assistant Professor, Department of Pathology, Greenlife Medical College. nailaawal@gmail.com
  2. Rezaul Karim Dewan, Professor and Head, Department of Pathology, Dhaka Medical College.
  3. Subrata Ray, Assistant Professor, Department of Pathology, Jessore Medical College.
  4. Jesmin Naz Ferdous, Assistant Professor, Department of Pathology, Sir Salimullah Medical College.

 *For correspondence

 Abstract

Background: The incidental findings may contribute to identify many common latent thyroid neoplasms. The study was carried out to evaluate the frequency of undiagnosed thyroid neoplasms existing in the general population of our country.
Methods: Total 200 whole thyroid glands were collected from the deceased who had apparently normal thyroid gland. The study includes 85 male and 115 female cadavers between 14 to 65 years of age. Sections were taken from grossly identified lesions for histopathological process, and studied microscopically, other areas were collected randomly for microscopic examination.
Result: In all cases, both benign and malignant neoplasms were incidental findings, seen in 4.5% of the cases. Malignant neoplasm was found in 2% of cases and was latent.
Conclusion: Clinically normal appearing thyroid glands may contain major pathological lesions, when they are microscopically studied. Considering the high prevalence of thyroid malignancy to other parts of the world, routine systematic examination of the gland is recommended to detect unsuspected thyroid pathology mainly carcinoma.

[Journal of Histopathology and Cytopathology, 2019 Jul; 3 (2):93-98]

 Key words: Occult neoplasm, thyroid


Introduction

Thyroid cancer is the fifth most common cancer in women worldwide.1 In most countries, incidence have been appreciably increasing over the last few decades.2,3 If recent trend is maintained, thyroid cancer may become the fourth most common cancer by 2030 in United States.4

Small “occult” thyroid carcinomas are present in a substantial proportion of the general population. In surgical practice, biopsy of thyroid without symptom is not indicated. So, autopsy sample can be an alternative to assess the incidence of latent thyroid neoplasms.

Usually, the thyroid gland is not examined in routine autopsies in Dhaka Medical College.  When a more careful and systematic study of the thyroid is done in autopsy material, latent thyroid lesions are found in a frequency of 20 times greater than the incidence seen at routine autopsy series (0.8 %).5 Pingitore R, (1982) found 3.6 % of latent carcinomas in his autopsy specimen.6 There is no data of unsuspected thyroid neoplasm after a systematic and histologic examination of the gland during autopsy in Bangladesh.

  The present study was designed to determine the frequency and evaluation of the prevalence of incidental carcinomas in our population in autopsy specimen. It may be of interest in regard to causal or prognostic factors.

Methods

This study was initiated after receiving approval of the ethical committee of our institution. It is cross-sectional descriptive study with convenient sampling done over a period of two years (January 2016 to December 2017). The study population comprised deceased undergoing medicolegal autopsy in morgue under the Forensic Medicine Department of Dhaka Medical College. The specimen was discarded if obtained from decomposed or mutilated body or when there was injury over the neck involving thyroid gland as well as from the subject in whom there was previous hemi thyroidectomy. Enlarged thyroid beyond normal range was also discarded from this study.

After receiving the specimen, it was fixed in 10% neutral buffered formalin and dissected free from surrounding neck tissues. The thyroid glands were weighed, measured and divided into right and left lobes with isthmus attached to one of lobes.

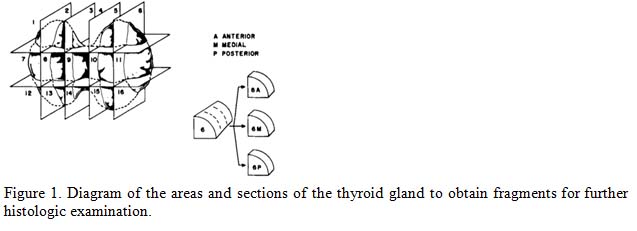
The whole thyroid gland was divided into three parts and labeled as anterior, middle and posterior from superior pole to inferior pole. The lobes were serially sectioned at 2 mm intervals from 16 areas of both lobes and isthmus.

Figure 1. Diagram of the areas and sections of the thyroid gland to obtain fragments for further histologic examination.

All grossly visible lesions were noted and many were photographed. Histological sections were made from all grossly visible lesions. If no gross lesions was identified at least one histologic section was prepared from each lobe of the glands and were processed. All the sections were stained with hematoxylin and eosin. The prepared slides were examined and the findings were noted. Special stain was donein selected cases.

Data was collected, compiled and properly tabulated in master chart. Representative tables and graphs were made and subjected to suitable statistical analysis by using appropriate methods.


Result

Among 200 cases, 85 cases (42.5%) were male and 115 cases (57.5%) were female. The male female ratio was 1: 1.36. The age of the study subject was 14 to 65 years with mean age 24.48± 12.09 years. The mean weight of thyroid gland was 15.50 ± 4.43 gm.

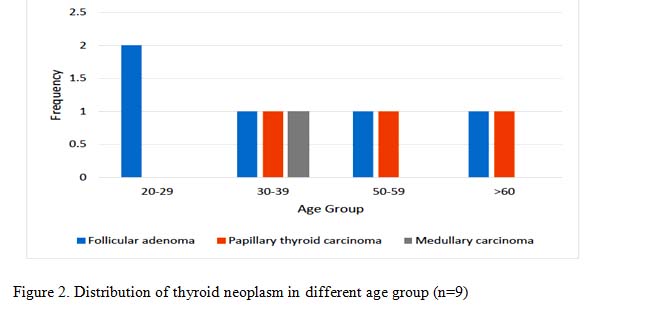
Neoplasm was seen in 9 cases out of 200 cases (4%). The youngest cadaver was 25 years and the oldest was 65 years of age. Major incidence occurred in 3rd decade. The most common neoplasm was follicular adenoma (5 cases, 2.5 %) followed by malignant neoplasm (4 cases, 2 %). The malignant neoplasm was papillary thyroid carcinoma and medullary thyroid carcinoma (1 case, 0.5%). All neoplasm was restricted to single lobe of thyroid except in one papillary thyroid carcinoma, where tumor foci were multiple involving left lobe and isthmus of thyroid

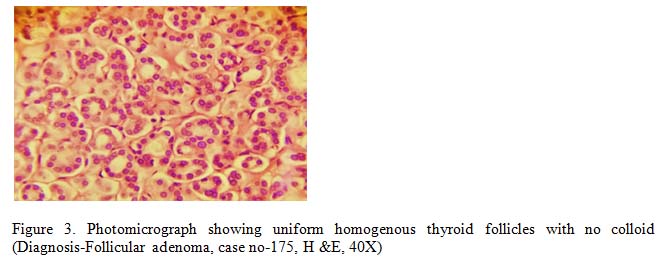
Follicular adenoma was the most common benign neoplastic lesion of solitary thyroid nodule. A total of 5 cases (3%) was diagnosed histologically as follicular adenoma, 3 cases were male and 2 cases were female. The size of the adenoma varied from 0.2 to 1.1 cm in diameter and had single foci distributed in single lobe of thyroid. Microscopically, they showed well demarcated areas consisting of numerous small uniform follicles with scanty colloid. The neoplastic cell showed follicular morphology. No capsular and vascular invasion was identified in any of the cases.

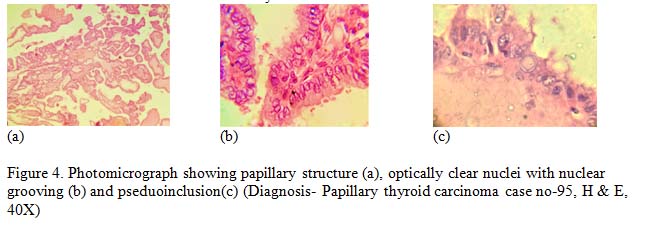
Among the malignant neoplasm, 3 cases (1.5%) were revealed as latent papillary thyroid carcinoma based on characteristic nuclear feature. None was encapsulated. All of these lesions were within 1 cm in maximum diameter. By definition, the tumors were diagnosed as papillary microcarcinoma.7 One of them was follicular variant of papillary carcinoma presented with ground glass appearance of nucleus and formation of follicles. Some of the neoplastic cells showed intranuclear groove. Psammoma bodies were not found in any cases.

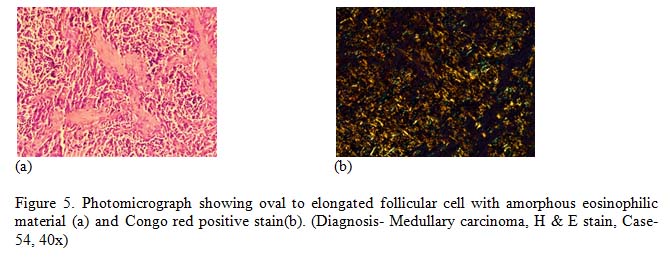
The only one case diagnosed as medullary carcinoma, composed of polygonal to spindle shaped cells forming nests. Acellular amorphous amyloid deposition was seen in stroma. Special stain Congo red was done and supported the diagnosis by green birefringence of amyloid.


Discussion

The incidental findings can contribute to discover many common thyroid lesions. The incidence of both benign and malignant lesions of thyroid varies widely in different geographical areas in the world.

This study was carried out with a view to evaluate the frequency of undiagnosed thyroid neoplasms existing in the general population of our country.

The incidence of thyroid carcinoma differs in different countries range from 0.5 to 10 per 105 persons.8 In most countries, papillary carcinoma was the most common histologic type, comprising approximately 40-70 % of all thyroid malignancy.8

In our study, the weight of thyroid gland with latent neoplasm (17.66 ± 4.03 gm) was similar to that of glands without neoplasm(15.39 ± 4.43 gm), because of we include apparently normal thyroid gland with normal weight. This correlates with previous study done by Ottino et al, (1989).9


The most common thyroid neoplasm of this study was follicular adenoma (3%, 5 cases) which is similar to the study done by Bisi, et al. (1989) which was 4.33%.10 Among the malignant neoplasms, one was medullary carcinoma and rest of three were papillary microcarcinoma. Papillary thyroid microcarcinoma is a specific subgroup of papillary thyroid carcinoma and defined by WHO on the largest dimension of 1.0 cm or less.7,11 Most of Papillary thyroid microcarcinoma are not detectable in clinical examination and are diagnosed incidentally during pathologic examination of thyroid specimens after surgery for benign thyroid diseases or in autopsies.11

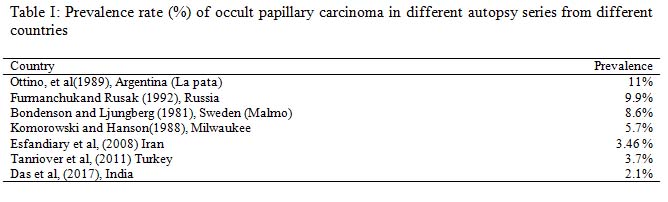
The rate of malignancy in this study was 2% (4 cases) whereas in a previous study done by das et al, (2017) the rate of malignancy was 2.1% (5 out of 240 cases) which is similar to our study.12 On the other hand, study done by Bondenson and Ljungberg (1981), they estimated rate of malignancy was 8.6 %.13 The higher prevalence of their study was probably due to large number of study subject. The study done by Furmanchuk and Rusak (1992), the estimated rate of malignancy was 9.9% (11 out of 122).14 The higher prevalence of their study was probably due to radiation and other hazard.14 Following tables show the prevalence rate (%) of occult papillary carcinoma in different autopsy series

 Conclusion

Many thyroid neoplasms may remain silent and diagnosed only autopsy during histopathological examination of specimen. So routine systematic examination of the gland is recommended to detect unsuspected thyroid neoplasm mainly carcinoma.

The presence of 2 % (4 cases out of 200) of malignant thyroid neoplasm in this study speaks about the burden of this disease in our population which may be detected by thorough thyroid screening test.

The latent thyroid diseases including thyroid carcinoma is treatable and have good prognosis. So, routine evaluation of thyroid status by thyroid function tests in a reasonable time interval can be done to evaluate the latent thyroid neoplasm. Routine systematic examination of thyroid gland during autopsy not only would be useful in determining the cause of death but also contribute to the social health data by yielding the frequency of latent thyroid neoplasm.

References

  1. Jemal A, Siegel R and Ward E. Cancer statistics 2010. A Cancer Journal for clinicians 2010; 60(5):277-300.
  2. Davies L, Welch HG. Increasing incidence of thyroid cancer in United States, 1973-2002, JAMA, 2006;295(18):2164-7.
  3. Horn-Ross PL, Lichtensztajn DY, Clarke CA, Dosiou C, Oakley-Girvan I, Reynolds P et al. Continued rapid increase in thyroid cancer incidence in California: trends by patient, tumor and neighborhood characteristics. Cancer Epidemitol Biomakersprev 2014; 23:1067-79.
  4. Rahib L, Smith BD, Aizenberg R, Rosenzweig AB, Fleshman JM, Matrisian LM. Projecting cancer incidence and deaths to 2030: the unexpected burden of thyroid, liver and pancreas cancers in the United States. Cancer Res 2014;74(11):2913-21.
  5. Silverberg SG and Vidone RA. Carcinoma of the thyroid in surgical and post-mortem material: Analysis of 300 cases at autopsy and literature review. Ann Surg 1966;164:291-299.
  6. Pingitore RR. Morfologiciautopticisu 111 tiroidiclinicamentenormali in un’ are aitalianasenzaedemiagozzigena. Purhologica 1982;14:545-552.
  7. Rosai J (2004). Rosai and Ackerman’s Surgical Pathology. 10th ed. St. Luis: Mosby.
  8. Harach HR, Franssila KO, Wasenius V. Occult Papillary Carcinoma of the Thyroid. A “Normal” Finding in Finland. A systematic Autopsy Study. Cancer, 1984; 108:529-530.
  9. Ottino A, Pianzola HM, Castelletto RH. Occult papillary thyroid carcinoma at autopsy in La Plata, Argentina. Cancer 1989;64:949-50.
  10. Bisi H, Fernandes VS, de Camargo RY, Koch L, Abdo AH, de Brito T. The Prevalence of Unsuspected Thyroid Pathology in 300 Sequential Autopsies, With Special Reference to the Incidental Carcinoma. Cancer 1989; 64:1888-1893.
  11. Dideban S, Abdollahi A, Meysamie A, Sedghi S, Shahriari M. Thyroid Papillary microcarcinoma: Etiology, clinical manifestations, Diagnosis, Follow-up, Histopathology and Prognosis. Iran J Pathol, 2016:11(1):1-19.
  12. Das MM, Jain BB, Sukul B, Chattopadhyay S. A histopathological study of autopsied thyroid. Thyroid Res Pract, 2017:14 (3):112-117.
  13. Bondenson L, Ljungberg O. Occult thyroid carcinoma at autopsy in Malmo, Sweden. Cancer, 1981;47:319-323.
  14. Furmanchuk AV, Rusak NI,(1992). Latent cancerous pathology of the thyroid. Vopr Onkol, 1992;38(7):811-7.

jhc-2019-v-3-n2-cytogenetic-baqui

Cytogenetic Pattern in Adult Patients with de novo Acute Myeloid Leukaemia: a Single Center Study in Bangladesh


*Baqi SA,1 Munmun UK,2 Khan MR,3 Shah MS,4 Islam S,5 Rahman F,6 Aziz MA,7 Begum M8


  1. Saqi Md. Abdul Baqi, Resident, Department of Haematology, Bangabandhu Sheikh Mujib Medical University, Shahbag, Dhaka. saqi.dmc@gmail.com
  2. Umme Kulsum Munmun, Lecturer, Department of Pathology, Dhaka Medical College, Dhaka.
  3. Md. Rafiquzzaman Khan, Associate Professor, Department of Haematology, Bangabandhu Sheikh Mujib Medical University, Shahbag, Dhaka,
  4. Md. Salahuddin Shah, Associate Professor, Department of Haematology, Bangabandhu Sheikh Mujib Medical University, Shahbag, Dhaka,
  5. Shafiqul Islam, Medical Officer, Department of Haematology, Bangabandhu Sheikh Mujib Medical University, Shahbag, Dhaka,
  6. Farzana Rahman, Assistant Professor, Department of Haematology, Bangabandhu Sheikh Mujib Medical University, Shahbag, Dhaka,
  7. Md. Abdul Aziz, Professor, Department of Haematology, Bangabandhu Sheikh Mujib Medical University, Shahbag, Dhaka,
  8. Masuda Begum, Professor, Department of Haematology, Bangabandhu Sheikh Mujib Medical University, Shahbag, Dhaka,


*For correspondence


Abstract

Background: Cytogenetic analysis performed at diagnosis is considered to be the most important prognostic factor in AML.

Objective: The purpose of this study was to observe the pattern of cytogenetic abnormalities in adult patients with de novo AML.

Method: Total fifty two newly diagnosed de novo AML patients were selected for the study. Six cytogenetic abnormalities including t(8;21), t(15;17), inv(16), BCR-ABL1, FLT3-ITD & NPM1 mutations were detected by Real-Time PCR.

Results: In this study, 36 (69.2%) patients showed different cytogenetic abnormalities. The t(15;17) was found to be the most common. t(15;17), t(8;21) and inv(16) were found only in M3, M2 and M4 subtypes, respectively. Significant association was found with increasing age and cytogenetic risk groups. BCR-ABL1 mutation showed significant relation with increased age. FLT3-ITD mutation showed significant association with increased WBC count and inv16 was significantly associated with relatively less bone marrow blast percentage.

Conclusion: So, Cytogenetic study should be performed routinely in all cases of AML for proper diagnosis, prediction of prognosis and implementation of effective therapeutic measures.


[Journal of Histopathology and Cytopathology, 2019 Jul; 3 (2):86-92]


Key words: Acute myeloid leukaemia, cytogenetics


Introduction

Acute myeloid leukaemia (AML) is a clonal, malignant disease of haematopoietic tissue which is characterized by accumulation of abnormal (leukaemic) blast cells, principally in the bone marrow, and impaired production of normal blood cells.1The incidence of AML is higher in the white population (3.8 per 100,000 person) than that of the Asian population (3.2 per 100,000 person).2 AML is the most common acute leukaemia in adult and it is more common in males. Majority of the AML patients are older than 60 years.3 Cytogenetic abnormalities were first described in AML in the 1960s.4 In 1988, the Morphologic, Immunologic and Cytogenetic (MIC) classification was published. Since then, cytogenetic investigations have become more important in AML classification.5 AML is heterogeneous in terms of morphology, immunophenotype, cytogenetics and molecular genetics.6 Using the WHO criteria, the diagnosis of AML is established by the presence of 20% or more of leukaemic myeloblasts in the peripheral blood or bone marrow. However, in a subgroup of AML, the presence of recurrent genetic abnormalities alone is sufficient for the diagnosis of AML regardless of the blast percentage.7 Geographical, ethnic, and environmental influences should be considered in determining the cytogenetic and morphological features of this disease.8 Cytogenetic abnormalities are identified in 50-60% of adult newly diagnosed AML patients.9 Age and cytogenetic abnormalities are the most important prognostic factors in AML.10There is an increase in the proportion of patients with unfavourable risk cytogenetics and a decrease in favourable risk cytogenetics with advancing age.11 Besides the prognostic importance, cytogenetic analysis is also recommended to monitor minimal residual disease (MRD) in case of AML patients with abnormal cytogenetics.12


From these points of view, the current study was designed to observe the pattern of cytogenetic abnormalities in adult patients with de novo AML, to categorize the patients into three risk groups and to observe the association of cytogenetic findings with FAB subtypes, age, sex & other laboratory findings.


Methods

This study was conducted in the department of Haematology, BSMMU from February 2018 to January 2019. Total fifty two newly diagnosed adult patients with de novo AML had been enrolled for the study. Complete blood count was done by automated cell counter machine and checked manually. Morphological diagnosis of AML had been done by bone marrow study. For cytogenetic study, 3-5 ml of peripheral blood or bone marrow aspirate was collected in EDTA tube. Six cytogenetic abnormalities including t(8;21), t(15;17), inv(16), BCR-ABL1, FLT3-ITD & NPM1 mutations were detected on an internationally standard laboratory by Real-Time PCR technique.The ABI 7500 real time PCR system (using the Taqman chemistry) was used for doing the cytogenetic analysis. A pre-designed semi-structured data collection sheet was used for data collection. The statistical analysis was carried out using the SPSS version 24.0 for Windows. For all statistical tests, p-value less than 0.05 was considered as statistically significant.


Results

The mean age of the patients was 36.87 (+13.29) years. Maximum (30.8%) patients belonged to 18-27 years age group. Female was slightly predominant with a male: female ratio was 1: 1.08. Maximum patients belonged to FAB M2 (32.7%), followed by M3 (26.9%) and M1 (17.3%). Among the 52 cases, 36 (69.2%) cases showed different cytogenetic abnormalities and 16 (30.8%) cases had normal cytogenetics. The t(15;17) was found to be the most common detected in 13(25%) patients. NPM1 mutation was found in 10 (19.23%), t(8;21) in 8 (15.38%) and FLT3-ITD mutation in 8 (15.38%) cases (Table I).


M0 and M6 subtypes did not show any cytogenetic abnormality. Most of the M1 cases also had normal cytogenetic pattern. The t(15;17), t(8;21) & inv16 were found only in M3, M2 & M4 subtypes respectively. Only one case showed BCR-ABL1 mutation which belongs to M1 subtype. A combination of NPM1 & FLT3-ITD mutation was found in M4, M1, M3 and M2 subtypes (Table II).


Significant association was found between the mean age of 78 years and BCR-ABL1 mutation (p value 0.038). Favourable cytogenetics were more frequent in younger age groups. Intermediate and unfavourable cytogenetics were common in relatively older age groups. These findings were statistically significant (p value 0.004).

FLT3-ITD mutation was significantly associated with increased WBC count (p value 0.042). inv(16) was significantly associated with relatively less bone marrow blast percentage (p value 0.029). Patients with normal cytogenetics showed significant association with relatively increased bone marrow blast percentage (p value 0.033). No other parameter (sex, haemoglobin level, platelet count) showed any significant association with cytogenetic pattern.

 Discussion

AML is characterized by a spectrum of clinical, morphological, immunophenotypic and associated cytogenetic abnormalities. In this study the mean age at presentation of AML was 36.87 years. Studies in most of the other countries showed much higher mean age.6,8,13,14,15 The reason for this difference may be due to inclusion of only de novo cases of AML in this study or may be geographic/ethnic influence.

Cytogenetic abnormalities were detected in 69.2% of patients with an increased frequency of t(15;17) in this study. These findings are consistent with the results of several other studies conducted by Ayesh et al. (2012)16 and Enjeti et al. (2004).13 Here, favourable cytogenetic risk group belonged to young patients and frequency of unfavourable cytogenetics were higher in older age groups. Similarly, Meng et al. (2013) found 75% favourable cytogenetics in young patients and mostly complex karyotype in elderly patients.6

Male: female ratio in this study was 1:1.08. This finding differs from most of the studies in other countries where male predominance was found.6,13,17This difference is probably due to greater proportion of female bed in our department. Geographic or ethnic influence may also be responsible. An increased frequency of t(15;17) (28%) was found among the male patients in this study. Enjeti et al. (2004) also found increased frequency of t(15;17) among male patients in a study from Singapore.13 No other significant difference was found in this study among male and female patients in relation to cytogenetics.

Cases with FLT3-ITD mutation were found in this study to have increased WBC count. Penget al. (2008) also demonstrated a correlation between the presence of FLT3 mutation and the increased WBC count.18 Similarly, Schnittger et al. (2002) and Haferlach et al. (2012) reported NPM1 and FLT3 mutations to be correlated with higher peripheral WBC count.19,20

The t(15;17) was found to be the most common (25%) cytogenetic abnormality in this study. The frequency of t(15;17) found in this study is much higher than other parts of Asia, like Taiwan (15%), compared to those observed in North America and Europe (3-10%).21,22 The t(15;17) was found in 85.7% of M3 subtype patients in the current study, which is very close to the findings in Singapore (82.5% of M3 patients)13, compared to Japan (75.4%)8 and Europe (72.5%).22

On the other hand, t(8;21) was found in 41.2% of AML M2 patients in this study. This percentage is closer to the incidence found in Japanese and Taiwanese reports (33.1% and 34% of their AML M2 patients).8,21 The t(8;21) is less frequent among  the AML M2 patients in Singapore (14.5%), Australia (15.3%) and North America (22%).13,23,24

In this study, significant difference was found in case of inv(16) pattern between M4 and non-M4 subtypes. Enjeti et al. (2004) also found the highest frequency of inv16 among their M4 cases.13

FLT3-ITD mutation was found more frequently in M4 subtype in this study. Similarly, another study carried out by Koczkodaj et al. (2016) in Southeastern Poland found the highest frequency of FLT3-ITD mutation in AML M4 cases.25 In an Iranian study, Rezaei et al (2017) divided the patients into FAB M3 and non-M3 groups and analyzed the FLT3-ITD and NPM1 mutational status among these patients. They also found that these mutations were more frequent in non-M3 patients.26 On the other hand, Smith et al. (2011) found a higher frequency of FLT3-ITD mutations among M3 patients.27


Falini et al. (2005) observed that FLT3-ITD mutations occur twice as often in the cases with simultaneous NPM1 mutations as in the cases without this mutation.28 The current study also shows that co-existent FLT3-ITD & NPM1 mutations are more frequent than FLT3-ITD mutation alone.

These differences in the frequency of cytogenetic/molecular genetic abnormalities might be due to geographic & ethnic heterogenecity, variation in the sample size or inclusion of paediatric patients in some studies. Paediatric patients were excluded in our study.

 Conclusion

Significant number of patients showed different cytogenetic abnormalities. Therefore, cytogenetic study should be performed routinely in all cases of AML for proper diagnosis, prediction of prognosis and implementation of effective therapeutic measures.

References

  1. Liesveld JL, Lichtman MA. Acute myelogenous leukemia. Williams hematology, 9th ed, Kaushansky K, Lichtman MA, Prchal JT, et al (Eds). McGraw-Hill Education; 2015:1373-1436.
  2. Howlader N, Noone AM, Krapcho M, Neyman N, et al. SEER Cancer Statistics Review, 1975–2009 (Vintage 2009 Populations), National Cancer Institute, Bethesda, MD, http://seeer.cancer.gov/csr/1975_2009_pops09/, based on November 2011 SEER data submission, posted on SEER web site 2012.
  3. Provan D, Baglin T, Dokal I, de Vos J. Oxford Handbook of Clinical Haematology. OUP Oxford; 2015 Apr 23:124-214.
  4. Greer JP, Arber DA, Glader B, List AF, Means RT, Paraskevas F, Rodgers GM. Wintrobe’s clinical hematology. Lippincott Williams & Wilkins; 2013 Aug 29:1585.
  5. Grimwade D, Walker H, Oliver F, Wheatley K, Harrison C, Harrison G, Rees J, Hann I, Stevens R, Burnett A, Goldstone A. The importance of diagnostic cytogenetics on outcome in AML: analysis of 1,612 patients entered into the MRC AML 10 trial. Blood. 1998 Oct 1;92(7):2322-33.
  6. Meng CY, Noor PJ, Ismail A, Ahid MF, Zakaria Z. Cytogenetic profile of de novo acute myeloid leukemia patients in Malaysia. International journal of biomedical science: IJBS. 2013 Mar;9(1):26.
  7. Vardiman JW, Thiele J, Arber DA, Brunning RD, Borowitz MJ, Porwit A, Harris NL, Le Beau MM, Hellström-Lindberg E, Tefferi A, Bloomfield CD. The 2008 revision of the World Health Organization (WHO) classification of myeloid neoplasms and acute leukemia: rationale and important changes. Blood. 2009 Jul 30;114(5):937-51.
  8. Nakase K, Bradstock K, Sartor M, Gottlieb D, Byth K, Kita K, Shiku H, Kamada N. Geographic heterogeneity of cellular characteristics of acute myeloid leukemia: a comparative study of Australian and Japanese adult cases. Leukemia. 2000 Jan;14(1):163.
  9. Mrózek K, Heerema NA, Bloomfield CD. Cytogenetics in acute leukemia. Blood reviews. 2004 Jun 1;18(2):115-36.
  10. Löwenberg BB. Diagnosis and prognosis in acute myeloid leukemia-The art of distinction. New England Journal of Medicine. 2008 May 1;358(18):1960-2.
  11. Shipley JL, Butera JN. Acute myelogenous leukemia. Experimental hematology. 2009 Jun 1;37(6):649-58.
  12. Marchesi F, Annibali O, Cerchiara E, Tirindelli MC, Avvisati G. Cytogenetic abnormalities in adult non-promyelocytic acute myeloid leukemia: a concise review. Critical Reviews in Oncology/Hematology. 2011 Dec 1;80(3):331-46.
  13. Enjeti AK, Tien SL, Sivaswaren CR. Cytogenetic abnormalities in de novo acute myeloid leukemia in adults: relation to morphology, age, sex and ethnicity-a single center study from Singapore. The Hematology Journal. 2004 Jan 1;5(5):419-25.
  14. Mauritzson N, Johansson B, Albin M, Billström R, Ahlgren T, Mikoczy Z, Nilsson PG, Hagmar L, Mitelman F. A single‐center population‐based consecutive series of 1500 cytogenetically investigated adult hematological malignancies: karyotypic features in relation to morphology, age and gender. European journal of haematology. 1999 Feb;62(2):95-102.
  15. Preiss BS, Kerndrup GB, Schmidt KG, Sørensen AG, Clausen NA, Gadeberg OV, Mourits‐Andersen T, Pedersen NT, AML Study Group Region of Southern Denmark. Cytogenetic findings in adult de novo acute myeloid leukaemia. A population‐based study of 303/337 patients. British journal of haematology. 2003 Oct;123(2):219-34.
  16. Ayesh M, Khassawneh B, Matalkah I, Alawneh K, Jaradat S. Cytogenetic and morphological analysis of de novo acute myeloid leukemia in adults: a single center study in jordan. Balkan Journal of Medical Genetics. 2012 Jan 1;15(1):5-10.
  17. Amare PK, Jain H, Kabre S, Deshpande Y, Pawar P, Banavali S, Menon H, Sengar M, Arora B, Khattry N, Narula G. Cytogenetic profile in 7209 Indian patients with de novo acute leukemia: a single centre study from India. J Cancer Ther. 2016 Jun 27;7:530-44.
  18. Peng HL, Zhang GS, Gong FJ, Shen JK, Zhang Y, Xu YX, Zheng WL, Dai CW, Pei MF, Yang JJ. Fms-like tyrosine kinase (FLT) 3 and FLT3 internal tandem duplication in different types of adult leukemia: analysis of 147 patients. Croatian medical journal. 2008 Oct 15;49(5):650-9.
  19. Schnittger S, Schoch C, Dugas M, Kern W, Staib P, Wuchter C, Löffler H, Sauerland CM, Serve H, Büchner T, Haferlach T. Analysis of FLT3 length mutations in 1003 patients with acute myeloid leukemia: correlation to cytogenetics, FAB subtype, and prognosis in the AMLCG study and usefulness as a marker for the detection of minimal residual disease. Blood. 2002 Jul 1;100(1):59-66.
  20. Haferlach T, Bacher U, Alpermann T, Haferlach C, Kern W, Schnittger S. Amount of bone marrow blasts is strongly correlated to NPM1 and FLT3-ITD mutation rate in AML with normal karyotype. Leukemia research. 2012 Jan 1;36(1):51-8.
  21. Tien HF, Wang CH, Lin MT, Lee FY, Liu MC, Chuang SM, Chen YC, Shen MC, Lin KH, Lin DT. Correlation of cytogenetic results with immunophenotype, genotype, clinical features, and ras mutation in acute myeloid leukemia A study of 235 Chinese patients in Taiwan. Cancer genetics and cytogenetics. 1995 Oct 1;84(1):60-8.
  22. Johansson B, Mertens F, Mitelman F. Geographic heterogeneity of neoplasia‐associated chromosome aberrations. Genes, Chromosomes and Cancer. 1991 Jan;3(1):1-7.
  23. Slovak ML, Kopecky KJ, Cassileth PA, Harrington DH, Theil KS, Mohamed A, Paietta E, Willman CL, Head DR, Rowe JM, Forman SJ. Karyotypic analysis predicts outcome of preremission and postremission therapy in adult acute myeloid leukemia: a Southwest Oncology Group/Eastern Cooperative Oncology Group Study. Blood. 2000 Dec 15;96(13):4075-83.
  24. Grimwade D, Walker H, Harrison G, Oliver F, Chatters S, Harrison CJ, Wheatley K, Burnett AK, Goldstone AH. The predictive value of hierarchical cytogenetic classification in older adults with acute myeloid leukemia (AML): analysis of 1065 patients entered into the United Kingdom Medical Research Council AML11 trial. Blood. 2001 Sep 1;98(5):1312-20.
  25. Koczkodaj D, Zmorzyński S, Michalak-Wojnowska M, Wąsik-Szczepanek E, Filip AA. Examination of the FLT3 and NPM1 mutational status in patients with acute myeloid leukemia from southeastern Poland. Archives of medical science: AMS. 2016 Feb 1;12(1):120.
  26. Rezaei N, Arandi N, Valibeigi B, Haghpanah S, Khansalar M, Ramzi M. FMS-like tyrosine kinase 3 (FLT3) and nucleophosmin 1 (NPM1) in Iranian adult acute myeloid leukemia patients with normal karyotypes: mutation status and clinical and laboratory characteristics. Turkish Journal of Hematology. 2017 Dec;34(4):300.
  27. Smith ML, Hills RK, Grimwade D. Independent prognostic variables in acute myeloid leukaemia. Blood reviews. 2011 Jan 1;25(1):39-51.
  28. Falini B, Mecucci C, Tiacci E, Alcalay M, Rosati R, Pasqualucci L, La Starza R, Diverio D, Colombo E, Santucci A, Bigerna B. Cytoplasmic nucleophosmin in acute myelogenous leukemia with a normal karyotype. New England Journal of Medicine. 2005 Jan 20;352(3):254-66.