
Correlation of Lymphovascular Density with Histological Prognostic Parameters in Gastric Carcinoma
*Hassan MI,1 Kabir AN,2 Poly FH,3 Ray S,4 Munmun UK,5 Mehjabin M6
- * Mohammed Imran Hassan, Assistant Professor (CC), Department of Pathology, National Institute of Diseases of Chest and Hospital, Mohakhali, Dhaka. imran.vua@gmail.com
- AKM Nurul Kabir, Associate Professor, Department of Pathology, BangabandhuSheikh Mujib Medical University, Shahbag,Dhaka.
- Ferdousi Hossain Poly, Medical Officer, OSD, DGHS, Attached- Department of Pediatric Neurology, National Institute of Neurosciences and Hospital, Dhaka.
- Subrata Ray, Assistant Professor, Department of Pathology, Jashore Medical College.
- Umme Kulsum Munmun, Lecturer, Department of Pathology, Dhaka Medical College, Dhaka.
- Monika Mehjabin, Lecturer, Department of Pathology, Shahid Suhrawardy Medical College, Dhaka.
*For correspondence
Abstract
Background: Carcinoma of the stomach is a major cause of cancer mortality worldwide. Gastric cancer is actually a curable disease if it is detected at an appropriate stage and treated adequately. It rarely disseminates widely before it has involved the lymph nodes and, therefore, there is an opportunity to cure the disease prior to dissemination. Tumor-induced lymphangiogenesis plays a crucial role in metastasis and tumor progression. However, the significance of lymph vessel density has been controversial in gastric cancer. Specific lymphatic markers are now available making possible analysis of lymphatic in cancer. The aim of this study was to investigate the relation of lymph vessel density with histological prognostic factors in gastric cancer as potential indicator.
Objectives: To estimate of the lymph vessel density using Podoplanin immunostain in gastric cancer and then to correlate lymph vessel density with histological prognostic factors.
Methods: Sections from Paraffin blocks of gastric adenocarcinoma with routine stain were assessed to detect prognostic factors and then assessed with immunostain Podoplanin to count lymph vessel density. The mean number of lymph vessels in five hot spots was calculated in both intratumoral and peritumoral areas. Finally correlation was seen between histological prognostic factors and lymph vessel density in gastric carcinoma.
Results: A positive significant correlation was found between lymph node metastasis with lymph vessel density in both intratumoral and peritumoral area. Similarly, a positive significant correlation was found between tumor stage with lymph vessel density in both intratumoral and peritumoral area.
[Journal of Histopathology and Cytopathology, 2020 Jan; 4 (1):12-22]
Keywords: Podoplanin, Lymphovascular density, Gastric carcinoma
Introduction
Carcinoma of the stomach is a major cause of cancer mortality worldwide. The prognosis of gastric carcinoma is poor with cure rates little better than 5–10%, although better results are obtained in Japan where the disease is common. Gastric cancer is actually a curable disease provided that it is detected at an appropriate stage and treated adequately. It rarely disseminates widely before it has involved the lymph nodes and, therefore, there is an opportunity to cure the disease prior to dissemination.1
Worldwide gastric cancer ranks fourth in frequency and second in cancer mortality rate; with a 5-year survival rate not exceeding 30% in Western countries.2 Gastric cancer incidence varies markedly with geography. In Japan, Chile, Costa Rica, and Eastern Europe the incidence is up to 20-fold higher than in North America, northern Europe, Africa, and Southeast Asia.1 The incidence of gastric carcinoma in Bangladesh is 5.2 per 100,000.3
Gastric cancer is a multi-factorial disease. Epidemiological studies point to a role for Helicobacter pylori, although its importance is disputed. Helicobacter pylori seem to be principally associated with carcinoma of the body of the stomach and the distal stomach rather than the proximal stomach. As Helicobacter is associated with gastritis, gastric atrophy and intestinal metaplasia, the association with malignancy is perhaps not surprising. Patients with pernicious anemia, gastric atrophy, duodenogastric reflux and reflux gastritis, intestinal metaplasia and cigarette smoking are at increased risk, as are those with gastric polyps. Diet appears to be important factor. The ingestion of substances such as spirits may induce gastritis and, in the long term, cancer. Excessive salt intake, deficiency of antioxidants and exposure to N-nitroso compounds are also implicated.1
The most useful classification of gastric cancer is the Lauren classification.4 In this system, there are principally two forms of gastric cancer: intestinal gastric cancer and diffuse gastric cancer. In intestinal gastric cancer, the tumor resembles carcinomas found elsewhere in the tubular gastrointestinal tract and forms polypoid tumors or ulcers. It probably arises in areas of intestinal metaplasia. In contrast, diffuse gastric cancer infiltrates deeply into the stomach without forming obvious mass lesions but spreading widely in the gastric wall.1
These tumors have several prognostic and predictive factors. The depth of invasion and the nodal and distant metastasis at the time of diagnosis remain the most important prognostic indicators for gastric carcinoma. Currently tumor size, nuclear grade and patient’s age are well known prognostic factors for patients with operable gastric cancer. These prognostic factors are widely used to determine whether to apply neo-adjuvant therapy in patient with gastric cancer. In advanced cases, gastric carcinoma may first be detected as metastases to the supraclavicular sentinel lymph nodes, also called Virchow’s node. Gastric carcinoma can also metastasize to the periumbilical region to form a subcutaneous nodule, termed as Sister Mary Joseph nodule. Local invasion into the duodenum, pancreas, and retroperitoneum is also characteristic. In such cases efforts are usually focused on chemotherapy or radiation therapy and palliative care. However, surgical resection remains the preferred treatment for gastric carcinoma.5
Lymphangiogenesis is a critical process for tumor growth, invasion and metastasis. That is why measurement of lymph vessel density may be clinically important in gastric cancer specimens. The induction of lymphangiogenesis by a tumor is controlled process, influenced by lymphangiogenic factors, which involve a complex interaction between tumor and endothelial cells.6 The pathologic approach to assess lymphangiogenesis involves microscopic estimation of lymph vessel density by using endothelial markers in immunohistochemistry.
On previous studies detection of lymphangiogenesis was limited due to lack of specific lymphatic endothelial markers. The recent discovery of anti-Podoplanin antibody has a major impact on lymphatic studies. Podoplanin has become a valuable marker for detecting lymph vessels and for identifying lymph vessel invasion in tumor.7
Podoplanin is a specific marker of the lymphatic endothelium and is not expressed in blood vessels. It is expressed by both developing and mature lymphatic endothelial cells and seems to be a more specific marker of lymphatic endothelial cells. By electron microscopy and immunoelectron microscopy, it was demonstrated that Podoplanin is mainly expressed on the luminal surface of lymphatic endothelial cells. Peritumoral (PT) lymphatic vessels are larger and more irregular than the intratumoral (IT) lymphatic’s, with a significantly lower density. Intratumoral lymphatic vessels are found in a large variety of tumors and are usually small, flattened and irregular. It was suggested that Podoplanin has potential role in invasion and metastasis of tumor. This hypothesis is mainly based on the observation that high expression of Podoplanin is consistently correlated with the presence of metastases. It was reported that Podoplanin expressing cells were found at the invasion.8 The use of an anti-Podoplanin-based therapeutic strategy could be suggested in the treatment of lymphatic metastases based on three considerations: (i) Podoplanin is a well-known marker of lymphatic endothelial cells; (ii) its expression seems to be associated with bad prognosis and high risk for lymph node metastases; (iii) it is involved in tumor invasion. In conclusion, Podoplanin is a sensitive marker of lymphatic endothelial cells and is very useful in evaluating lymphatic micro vessel density. Immunohistochemical detection of Podoplanin is helpful in the diagnosis of lymphovascular invasion.8 Some studies have suggested that lymph vessel density is associated with an increased risk of lymph node metastasis;9 however, this conclusion is not supported by all of the published studies.10


The study was conducted a) to investigate morphological prognostic factors of gastric adenocarcinoma, b) to estimate lymph vessel density by using immunostain Podoplanin and c) to correlate lymph vessel density with prognostic factors.
Methods
It was a cross sectional observational study carried out from March, 2016 to July, 2018at the Department of Pathology, Bangabandhu Sheikh Mujib Medical University (BSMMU), Dhaka, Bangladesh. The study population was paraffin blocks of gastric adenocarcinoma from pathological laboratory in the same Institute with consecutive convenience sampling. Inclusion Criteria was paraffin blocks of gastric samples diagnosed as gastric adenocarcinoma in pathology laboratory and Exclusion criteria were with history of treated gastric carcinoma cases like neo adjuvant therapy, blocks containing autolyzed tissue, extensive necrosis, hemorrhage and desmoplasia, blocks having no tissue or damaged blocks and blocks containing other cancers like lymphoma, carcinoid tumor, malignant GIST etc. The sample size was 53. Monoclonal Anti-Human Podoplanin antibody, clone D2-40, Ready to use (code- IR072) was used for detecting lymph vessel. In this study, sections of normal vermiform appendix were taken as positive control (as recommended by Dako). Podoplanin antigen expression was detected by immunohistochemistry in the submitted blocks (paraffin blocks with maximum tumor bulk were chosen) and were performed using DAKO Cytomation at immunohistochemistry laboratory, department Pathology, BSMMU.
Histopathological categorization of tumor and grading of all the cases were done. Lymphovascular invasion was recorded. Each lymph node was histologically examined to determine metastasis. Numbers of lymph vessels were counted by Weidner’s method in peritumoral (PT) and intratumoral (IT) areas.11
Micro vessel Quantification
Determination of lymph vessel density (LVD) were performed according to Weidner et al.11Brown staining of cytoplasmic membrane of endothelial cells of lymph vessels were considered as positive reaction. Lymph vessel density was calculated according to Weidner’s method by Olympus microscope model BH51. The immunostained sections were scanned by light microscopy at low magnification (10x) and the areas of tissue with the greatest numbers of distinctly highlighted lymph vessels (“hot spots”) were selected. So, “hot spot” is an area with the most dense lymph vessels growth. Five hot spots were selected in intratumoral (IT) and peritumoral (PT) areas. When the hot spots were defined, lymph vessel count were performed by counting the individual stained lymph vessel (at power 20x) representing a field size of 0.74mm2 (i.e. – 20x objective lens, 10x ocular lens; equivalent to 0.7386 mm2 per 200x field).11 The mean number of lymph vessels in each case were determined and considered as the lymph vessel density.7So, at first five hot spots were chosen in intratumoral (IT) and peritumoral (PT) area. In each hot spot, lymph vessel count was performed at power x20. Finally lymph vessel density was calculated as the mean of the total number of lymph vessels in these five hot spots. Lymph vessel density (LVD) assessed in this manner may be not equivalent to LVD seen in multiple areas of multiple samples of the stomach; however, it is well accepted that these hot spots, not arbitrary areas, are representative of the entire tumor. Although there is some variability in the distribution of lymph vessels within the layers of the gastric wall, the five ‘hot spot’ areas were chosen to obtain an objective assessment and to avoid observer variation.7

Results
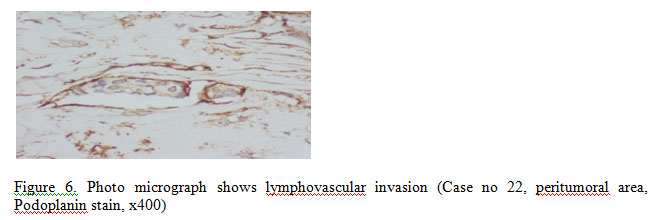
A total number of fifty three diagnosed cases of gastric adenocarcinoma were taken for this study. Forty six samples were partial/subtotal gastrectomy specimen and seven samples were total gastrectomy specimen. All fifty three samples contain epigastric lymph nodes ranging one to twenty five. Thirty seven cases had lymph node metastasis and the rest sixteen were free of tumor metastasis. Thirty seven cases were LVI positive in H&E routine stain and forty two cases were LVI positive with Podoplaninimmunostain.
In the group of 53 patients with gastric carcinoma, mean patients’ age was 49.87±11.38 years (range 20-70).33 patients ware male and 20 patients ware female with a male/female ratio of 1.6:1. According to Lauren’s classification, 30 cases ware diffuse type and 23 cases were intestinal type. Two third (60.4%) samples belonged to tumor size ≤ 5 cm. The mean tumor size was 5.61±1.92 cm, ranged from (3.0 – 11.0) cm. Lymph vessel density (LVD) was more frequent in cases having tumor size > 5 cm in diameter.
The histological grade was assessed according to WHO grading system. 33(62.3%) samples belonged to grade-III (poorly differentiation), followed by grade-II (moderate differentiation) (24.5%) and grade-I (well differentiation)(13.2%). Lymph vessel density (LVD) was most frequent in grade- II group.
Cases were grouped according to depth of invasion (tumor stage) as T1, T2, T3 and T4. 41.5% samples belonged to subserosal invasion (T3). T3 was followed by T2(32.1%), T4 (20.8%) and T1(5.7%). Lymph vessel density(LVD) was most frequent in T3 group.
Numbers of lymph node ranged from 1-25. Cases were grouped according to the numbers of lymph node metastasis as N0, N1, N2 and N3. 30.2% samples had no lymph node metastasis (nodal stage N0). 28.3% samples belonged to nodal stage N1, followed by nodal stage N2 (20.8%) and N3 (20.8%). Nodal stages were increasing with increase of Lymph vessel density (LVD).
Lymph vessels in intratumoral (IT) area ranged from 1-12 and peritumoral (PT) area ranged 2-11. Mean LVD in IT area was 5.93 ±2.79 cm and mean LVD in PT area was 5.50±2.38 cm.
A positive correlation was found between Lymph vessel density(LVD) and tumor stage in intratumoral (IT) area (Figure 7).
The value of Pearson’s correlation coefficient was 0.377 and it was significant (p=0.005). Therefore, there was linear association between tumor stage and lymph vessel density (LDV) in intratumoral (IT) area with Podoplanin stain.

A positive correlation was found between Lymph vessel density(LVD) and tumor stage in peritumoral (PT) area (Figure 8). The value of Pearson’s correlation coefficient was 0.334 and it was significant (p=0.014). Therefore, there was linear association between tumor stage and lymph vessel density (LVD) in peritumoral (PT) area with Podoplanin stain.

A positive correlation was found between Lymph vessel density (LVD) and Lymph node metastases inintratumoral (IT) area (Figure 9).
The value of Pearson’s correlation coefficient was 0.855 and it was significant (p=0.000). Therefore, there was linear association between lymph node metastasis and lymph vessel density (LVD) in intratumoral (IT) area with Podoplanin stain.

A positive correlation was found between Lymph vessel density (LVD) and Lymph node metastases in peritumoral (PT) area (Figure 10).
The value of Pearson’s correlation coefficient was 0.791 and it was significant (p=0.000). Therefore, there was linear association between lymph node metastasis and lymph vessel density (LVD) in peritumoral (PT) area with Podoplanin stain.

A positive correlation was found between LVD in IT and PT.
The value of Pearson’s correlation coefficient was 0.937 and it was significant (p=0.000). Therefore, there was linear association between LVD in intratumoral (IT) and peritumoral (PT) area with Podoplanin stain.
Discussion
Gastric carcinoma is the most common leading tumor of the world. Although great efforts have been made in the field of early diagnosis and adjuvant therapy, the incidence and overall mortality of gastric carcinoma continues to increase. Since gastric tumor cells commonly infiltrate into the lymphatic system, lymph node status is routinely used to identify a patient’s prognosis, tumor stage, and treatment modality. Inhibition of tumor cells to lymph node metastasis (LNM) is a promising way to prevent distant metastasis. However, the relationship between lymphangiogenesis, lymphovascular invasion and lymph node metastasis (LNM) remains ambiguous.
This cross sectional study was carried out with an aim to estimate the density of expression of Podoplanin in lymphangiogenic vessel in gastric adenocarcinoma and to see the correlation between the percentages of area covered by lymphangiogenic vessels with prognostic factors. The present study findings were discussed and compared with previously published relevant studies.
In this study, 62.3% sample had grade-III (poorly differentiation) followed by 24.5% grade-II (moderately differentiation) and 13.2 % grade-I (well differentiation). Significant relation was found between lymph vessel density-intratumoral (LVD-IT) area (p=0.013) and lymph vessel density-peritumoral (LVD-PT) area (p= 0.006) with different histological differentiation. In their study, Pak et al., 201512 found that 53.3 % sample had grade-III and significant relation (p= 0.021) between LVD-IT area with histological differentiation, which is comparable with the current study.
It was observed that 41.5 % of samples belonged to T3, followed by 32.1% T2, 20.8% T4 and 5.7% T1 and significant relation found between LVD-IT area (p=0.019) and LVD-PT area (p=0.041) with different tumor stage. Gresta, Rodrigues Jr and Cabral, 201413 found 63.5% cases were T3, followed by 19.2% T2, 13.4% T1 and 3.8% T4. Pak et al., 2015 found 39.3% samples were T3 followed by 16.6 % T2 and T4. They also found significant association between LVD-IT area (p=0.024) with different tumor stage. Raica et al., 20088 found significant correlation between LVD with tumor stage (p<0.002) and Nakamura et al., 20067 found significant positive correlation between LVD with tumor stage (p=0.0008). So, present study result is consistent with previous study.
According to number of lymph node metastasis (LNM), it was observed that 30.2% sample belonged to nodal stage 0 (N0), followed by 28.3% stage-I (N1), 20.8% stage II (N2) and stage III (N3). There was significant relation was found between LVD-IT area (p<0.001) and LVD-PT area (p<0.001) with nodal status. Yan et al., 200814 reported that LVD was obviously higher in the colorectal cancer sample with metastasis (12.08 ± 4.96) than in those without (8.26 ± 4.08) (p<0.001). Schoppmann et al., 200115 demonstrated that lymph vascular invasion (LVI), assessed by anti-Podoplanin immunostain, has been strongly associated with presence of lymph node metastasis. Pak et al. 201512 found LVD-IT area was a higher than LVD-PT area (12.29± 4.36 vs. 11.01±3.62), Nodal stage N0 cases were more frequent and significant relation between LVD-PT in area (p=0.040) with nodal status. Nakamura et al., 20067 found significant positive correlation between LVD with nodal metastasis (p= 0.0094). Raica et al., 20088 found significant correlation between LVD with nodal metastasis (p<0.031) which is comparable with current study.
In this study, there was a positive significant Pearson’s correlation (r= 0.855, p= 0.000) was found between lymph node (LN) metastasis with LVD in IT area. Similarly, there was a positive significant Pearson’s correlation (r= 0.791 p= 0.000) was found between LN metastasis with LVD in PT area. Pak et al., 201512 found in their study that LVD in PT area was significantly associated with LN metastasis (p=0.040). Nakamura et al., 20067 found significant correlation between LN metastasis with LVD (p= 0.0094). Raica et al., 20088 reported that there was significant positive correlation between both LVD in IT and PT areas with LN metastasis (P<0.031). So current study result is consistent with previous study.
In this current study, there was a positive significant Pearson’s correlation (r= 0.377, p= 0.005) was found between tumor stages with LVD in IT area. Similarly, there was a positive significant Pearson’s correlation (r= 0.334, p= 0.014) was found between tumor stage with LVD in PT area. Nakamura et al., 20067 found significant positive correlation between tumor stage with LVD (p= 0.0008). Raica et al., 20088 reported that there was significant positive correlation between both LVD-IT area and LVD-PT area with tumor stage (P<0.02).
In this current study, there was a positive significant Pearson’s correlation (r= 0.937, p= 0.000) was found between LVD-IT areas with LVD-PT areas. Pak et al., 201512 found significant correlation (p=0.028) between LVD-IT area with LVD-PT area.
Conclusion
Total fifty three cases of gastric adenocarcinoma were examined for lymphangiogenic vessels in peritumoral (PT) and intratumoral (IT) areas. Thirty seven cases had lymph node metastasis and the rest sixteen were free of tumor metastasis. Both peritumoral and intratumoral lymphangiogenic vessel count (density) stained by Podoplanin antibody correlated with lymph node metastasis and tumor stage. Lymphatic vessel count is more in the intratumoral area. The specific lymphatic endothelial marker Podoplanin proved to be a valuable tool in highlighting lymph vessel density (LVD) and lymphovascular invasion, and therefore a predictor of lymph node metastasis.
Limitation
The study population was selected from one institute in Dhaka city, so that the results may not be reflect the exact picture of the country. The study period was short. Sample size was small. Podoplanin was only marker used to detect lymph vessels. Sometimes differentiation between blood vessels and lymph vessels were difficult in tissue sections. Differentiation between blood vessels and lymph vessels was also a limitation of this study. Use of blood vessel immunostain like factor VIIIa, CD31, and CD 34 etc. could have overcome the limitation and overall no control was used.
References
- Williams NS, Bulstrode CJ, O’connell PR. Bailey & Love’s short practice of surgery. Crc Press; 2008. pp.450-456.
- Carl-McGrath S, Ebert M, Röcken C. Gastric adenocarcinoma: epidemiology, pathology and pathogenesis. Cancer therapy. 2007; 5(2):877-94.
- Rahman R, Asombang AW, Ibdah JA. Characteristics of gastric cancer in Asia. World journal of gastroenterology: WJG. 2014;20(16):4483.
- Lauren P. The two histological main types of gastric carcinoma: diffuse and so called intestinal type carcinoma: an attempt at a histoclinical classification. Acta Pathologica Microbiologica Scandinavica. 1965; 64(1):31-49.
- Kumar V, Abbas AK, Fausto N, Aster JC. Robbins and Cotran pathologic basis of disease, professional edition e-book. elsevier health sciences. 2014 Aug 27. pp.760-777.
- Joo YE, Sohn YH, Joo SY, Lee WS, Min SW, Park CH, Rew JS, Choi SK, Park CS, Kim YJ, Kim SJ. The role of vascular endothelial growth factor (VEGF) and p53 status for angiogenesis in gastric cancer. The Korean journal of internal medicine. 2002; 17(4):211.
- Nakamura Y, Yasuoka H, Tsujimoto M, Kurozumi K, Nakahara M, Nakao K, Kakudo K. Importance of lymph vessels in gastric cancer: a prognostic indicator in general and a predictor for lymph node metastasis in early stage cancer. Journal of clinical pathology. 2006; 59(1):77-82.
- Raica M, Ribatti D, Mogoanta L, Cimpean AM, Ioanovici S. Podoplanin expression in advanced-stage gastric carcinoma and prognostic value of lymphatic micro vessel density. Neoplasma. 2008;55(5):455-60.
- El-Gohary YM, Metwally G, Saad RS, Robinson MJ, Mesko T, Poppiti RJ. Prognostic significance of intratumoral and peritumoral lymphatic density and blood vessel density in invasive breast carcinomas. American journal of clinical pathology. 2008;129(4):578-86.
- Zhao YC, Ni XJ, Li Y, Dai M, Yuan ZX, Zhu YY, Luo CY. Peritumorallymphangiogenesis induced by vascular endothelial growth factor C and D promotes lymph node metastasis in breast cancer patients. World journal of surgical oncology. 2012;10(1):165.
- Weidner N, Folkman J, Pozza F, Bevilacqua P, Allred EN, Moore DH, Meli S, Gasparini G. Tumor angiogenesis: a new significant and independent prognostic indicator in early-stage breast carcinoma. JNCI: Journal of the National Cancer Institute. 1992;84(24):1875-87.
- Pak KH, Jo A, Choi HJ, Choi Y, Kim H, Cheong JH. The different role of intratumoral and peritumoral lymphangiogenesis in gastric cancer progression and prognosis. BMC cancer. 2015; 15(1):498.
- Gresta LT, Júnior IA, Cabral MM. Micro vessel density quantification in gastric cancer: comparing methods for standard measures. J Cancer SciTher. 2014;6(10):401-5.
- Yan G, Zhou XY, Cai SJ, Zhang GH, Peng JJ, Du X. Lymphangiogenic and angiogenicmicrovessel density in human primary sporadic colorectal carcinoma. World Journal of Gastroenterology: WJG. 2008; 14(1):101.
- Schoppmann SF, Birner P, Studer P, Breiteneder-Geleff S. Lymphatic microvessel density and lymphovascular invasion assessed by anti-podoplanin immunostain in human breast cancer. Anticancer research. 2001; 21(4A):2351-5.


