Comparison between Bethesda System and Conventional System for Standardization of Reporting Thyroid Cytopathology

Comparison between Bethesda System and Conventional System for Standardization of Reporting Thyroid Cytopathology

 *Saleheen S,1 Rahman DA,2 Chowdury MA,3 Haque MM,4 Habib S,5 Khan KH6


  1. * Saied Saleheen, Assistant Professor, Department of Pathology, Sheikh Hasina Medical College, Tangail. saleheen44@gmail.com
  2. DM. Arifur Rahman, Assistant Professor, Department of Pathology, TMSS Medical College, Gokul, Bogura,
  3. Mehdi Ashik Chowdury, Assistant Professor, Department of Pathology, Jahurul Islam Medical College, Bajitpur, Kishoreganj.
  4. Mohammad Mahbubul Hoque, Lecturer, Department of Pathology, Sheikh Sayera Khatun Medical College, Gopalganj.
  5. Saequa Habib, Associate Professor, Department of Pathology, Bangabandhu Sheikh Mujib Medical University, Dhaka.
  6. Kamrul Hasan Khan, Professor, Department of Pathology, Bangabandhu Sheikh Mujib Medical University, Dhaka.

 *For correspondence

Abstract

Background: Fine-needle aspiration cytology (FNAC) is considered as an effective test to screen and diagnose patients with thyroid swelling for surgical management. But FNAC still suffers because of its inherent limitations as well as variability in its diagnostic terminology.The Bethesda System of Reporting Thyroid Cytopathology (TBSRTC) may improve the state. This study was to report the experience in using this reporting system to redistribute the cytological diagnoses made by conventional system and also to evaluate the specificity, sensitivity, accuracy and predictive values as a tool to compare both the methods based on the correlation between cytopathology and histopathology.

Methods: A total of 73 patients presenting with thyroid swelling were subjected to FNAC and reporting was done according to the conventional system and TBSRTC. The cytological diagnosis was correlated with the histopathological diagnosis. The sensitivity, specificity, predictive values were calculated considering cytology as screening test.

Results: In this study, TBSRTC was found superior because of higher sensitivity (91.66%) and specificity (97.77%) as compared to conventional system (80.76% and 87.23% respectively). Positive predictive value, negative predictive value and diagnostic accuracy of Bethesda system were 95.65%, 95.65% and 90.41% respectively which were also significantly higher as compared to those of conventional system (77.78%, 89.13% and 84.93% respectively).

Conclusions: TBSRTC may improve the efficacy of thyroid FNAC as a screening test.

 [Journal of Histopathology and Cytopathology, 2020 Jan; 4 (1):38-47]

 Keywords: Comparison, Thyroid FNAC, Bethesda system (TBSRTC), Conventional system, Histopathology, Standardization

Introduction

Fine Needle Aspiration Cytology (FNAC) is a quick, cost-effective and minimally invasive outpatient procedure used worldwide in the initial diagnosis of thyroid swellings. As it can distinguish between benign and malignant lesions quite effectively, it is the preoperative screening method of choice worldwide.1 Before the routine use of thyroid Fine Needle Aspiration (FNA), the percentage of surgically resected thyroid nodules that were malignant was 14%.2 With current thyroid FNA practice, the percentage of resected nodules that are malignant surpasses 50%.3

However, due to the lack of a standardized system of reporting, pathologists have been using different terminologies and diagnostic criteria, leading to confusion amongst clinicians in the interpretation of the cytopathology report and ultimately hindering a definitive clinical management.4 It has also hindered the sharing of clinically meaningful data among multiple institutions.5 To mitigate this confusion all the pathologists need to use the same diagnostic criteria and terminology.6

Various reporting formats of thyroid FNAs have been suggested in the literature since the 1970s when thyroid FNAs began to be the subject of publications, and new formats continued to emerge.7 Several classification schemes have been suggested by various authors based on personal/institutional experiences but there is general support for the utilization of a tiered classification system.5 With this background, the National Cancer Institute (NCI), Bethesda, Maryland, United States, published an atlas and guidelines using standardized nomenclature for the interpretation of thyroid FNAC known as The Bethesda System for Reporting Thyroid Cytopathology (TBSRTC).4 It categorized the thyroid FNAC diagnoses into six groups with well-defined cancer risk and clear indications for further clinical management.8 It has also increased the interobserver reproducibility of cytopathological diagnoses of thyroid lesions.9-12

TBSRTC has been well received by both pathologists and clinicians and has been widely implemented by pathology laboratories in USA and in several European countries.13 Following publication of TBSRTC, the reporting system used in the United Kingdom since 2002, was updated by a working group of The Royal College of Pathologists and is now quite similar to TBSRTC.14 But TBSRTC still has to go a long way in getting acceptability in many countries of Asia and Africa.10

A good number of studies have been carried on in several countries in Asia (India, Pakistan, Iran, Korea and KSA) regarding usefulness of TBSRTC and it has been proved useful for management of patients with thyroid swelling in these countries.9,11,15-20 But this relatively recent six category scheme still needs to be validated by more prospective studies with histopathological correlation.16

In Bangladesh, there is no known reporting scheme using tiered classification system. The utility of thyroid cytopathology reporting according to TBSRTC in context of Bangladesh is also unexplored. Standardization of the reporting system by TBSRTC may result in improvement of the quality, homogenization and also reduce interobserver variability of thyroid cytopathology reports. In this context, this study was performed to assess the predictive values, sensitivity and specificity and accuracy of the TBSRTC in comparison with that of the conventional system used in the BSMMU, Dhaka, Bangladesh with histopathological correlation. The view was to observe the usefulness of Bethesda system for standardization of thyroid cytopathology reporting in the context of this country (Bangladesh).

 Methods

This is a cross sectional study carried out at the Department of Pathology, Bangabandhu Sheikh Mujib Medical University (BSMMU), Dhaka during the period from March 2015 to February 2017. A total of 73 patients presenting with thyroid swelling were included in this study, who has undergone FNA followed by the biopsy of the thyroid lesions. Patients presenting with thyroid swelling in any lobe of thyroid detected by clinical palpation (multinodular, solitary nodule, diffuse goiter etc) were included except those unwilling to be involved into the study.

All clinical information were recorded in a pre-designed proforma including demographic features, address and telephone contacts (for histological follow up). Results of all the routine investigations with special attention to ultrasonography of neck, serum T3, T4, and TSH levels and thyroid scintigraphy were noted where available.     

FNA of all patients was performed at the Department of Pathology, BSMMU.  Smears were stained with Papaniculaou (PAP) and Hematoxylin and Eosin (H&E) stains. Cytological findings were recorded and diagnoses were made according to both conventional and TBSRTC for each cases. For the TBSRTC reporting the Atlas10was used as manual (Table I). Reports were issued according to conventional method.

Koss’ Diagnostic Cytology and its histopathologic bases21 was followed conventionally as reference book in this department. The diagnoses made by conventional system are mostly based on its reference. The diagnoses were: Non-neoplastic lesions: Nodular goiters (NG) including cystic degeneration (CD), Lymphocytic thyroiditis (LT), Hashimoto thyroiditis (HT), Nodular goiter with co-existent thyroiditis, Multinodular goiter (MNG).

 Cellular follicular lesion (CFL): Cellular smears on cytology that included goiters with adenomatous changes, follicular adenomas and carcinomas, as well as the follicular variant of papillary carcinomas. In BSMMU suspicious cytology, atypia of undetermined significance and other gray zone cytology are also included within this diagnosis.

 Neoplastic lesions: Papillary thyroid carcinoma (PTC), suggestive of papillary carcinoma, medullary thyroid carcinoma (MTC) etc.

Biopsy specimens or histopathological reports of the patients undergoing surgery following the FNA interpretation under this study were collected. The histopathological findings were correlated with cytopathological findings and were recorded accordingly.

Descriptive analytical statistics was calculated. Thyroid FNA was considered as a ‘screening test’ and histopathology as gold standard. FNA benign was considered to be negative and the remaining categories were considered to be positive because they indicated significant risk of malignancy and led to a recommendation of surgery.8 Sensitivity, specificity, accuracy, the positive predictive value (PPV) and negative predictive value (NPV) were calculated from the available data by statistical formulae. In this study, Thyroid FNA has been considered as a screening method as TBSRTC is formed by NCI as a screening method to triage the patients effectively into groups that need surgery and the other that do not.5

For calculating statistical parameters nondiagnostic (ND) and AUS/FLUS cases were excluded as non-definitive diagnoses and categories, SFM and malignant were put together in most of the studies.15,16,22-24 In this study, the inadequate/ND cases were reaspirated and have been included rationally in other categories. Those which were still inadequate, had been excluded from statistical analysis.

 Results                                                                                                                          

Out of the 73 cases 62(84.9%) were female and 11(15%) were male. The age of the patients ranged from 16 to 70 years with average age around 40 years.

According to the conventional system forty five (61.64%) cases were diagnosed nodular goiter. Five (11.11%) of these lesions were found to be neoplastic (one benign and 4 malignant) on histopathology. Although all PTC and suggestive of PTC categories were found neoplastic and also malignant, 60% of the cellular follicular lesions (9 out of 15) were neoplastic (one benign and 8 malignant) and the rest were benign on final histological diagnosis.

The lesions when redistributed according to the Bethesda system: 46 (63%), 04 (5.4%), 03 (4.1%), 08 (10.95%), 12(16.4%) of the lesions were diagnosed as Cat-II, Cat-III, Cat-IV, Cat-V and Cat-VI respectively. The redistribution of the lesions after application of Bethesda system is shown in Table-II.
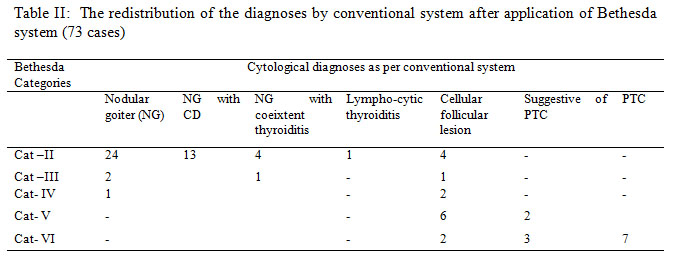
Out of 73 cases, 64 (22 neoplastic and 42 non-neoplastic) cytological diagnoses were concordant on both the conventional and Bethesda systems. One lesion was non-neoplastic on conventional but diagnosed neoplastic on Bethesda system while 04 neoplastic lesions by conventional system were categorized as non-neoplastic by Bethesda system. Three non-neoplastic and one neoplastic case according to conventional system were categorized as Cat- III (AUS) by Bethesda system. The CFL on conventional system were distributed by the Bethesda system into various categories that matched well (Table-III) with final histological diagnoses.

All the neoplastic lesions irrespective of benign and malignant neoplasm were considered positive for both the histological and cytological diagnoses, as they recommend for surgical excision. The concordances of the cytological diagnoses made by two methods with the final histological diagnoses are shown in Table IV.

Granulomatous thyroiditis: GT, Follicular adenoma: FA, Follicular carcinoma: FC, FVPTC: Follicular Variant of PTC, WDTUMP: Well differentiated tumor of uncertain malignant potential.

Diagnoses made according to TBSRTC shows increased overall concordance with hisotoathological diagnosis than that of the conventional system.

FNA interpretation by conventional method yielded significant false positive (6) and false negative (5) diagnoses. While analyzing the smears by the Bethesda system had decreased both the false positive (1) and false negative (2) interpretations. The sensitivity, specificity, accuracy and predictive values calculated for both the methods by using the statistical formulas are compared to each other in the Table V.

Sensitivity and positive predictive value (PPV) of the Bethesda system were found better (91.66% and 95.65% respectively) when compared to that the conventional system (80.76% and 77.78% respectively). The specificity and negative predictive values (NPV) were also found higher for Bethesda system (97.77% and 95.65%) in comparison to that of the conventional system (87.23% and 89.13% respectively). Diagnoses according to the Bethesda categories were 90.41% accurate where accuracy for the conventional system was 84.93%.

 Discussion

Reporting according to the conventional system included 41 (about 56.16%) patients into benign category, while category-II (Benign) in the Bethesda system included 44 (60.27%) patients. All (12) the suspicious for malignancy and malignant diagnoses on conventional system corresponded to category V and VI of Bethesda system. It reflects that there was actually no significant change in diagnosis of unequivocally benign and malignant cases according to the two systems of reporting.

15 (20.54%) CFL diagnosed by conventional system was the major field where the Bethesda system varied markedly. So, CFL was a “gray zone” diagnosis that included some benign (26.67%) and malignant (53.33%) cases.25 These cases when reclassified by the Bethesda system yielded more specific results with good histological correlation (Table IV). This difference can be explained by- i) Subjective underscoring of some neoplastic cytologies which are of SFM category in more objective Bethesda system and  ii) Assigning the follicular lesion diagnosis for some hyper cellular smears of goiter arranged in folded sheet appearance.

The 06 false-positive FNA diagnoses in conventional system included cellular smears of histologically nodular goiters that were interpreted as CFLs. Four of these cases were interpreted benign (category-II) by Bethesda system and 01 case was designated category-IV (suspicious for Hurthle cell neoplasm) because of relative abundance of Hurthle cells showing pleomorphism. Five cases were false negative for conventional method, 04 of which were due to compromised cytology samples. The rest one case diagnosed conventionally as nodular goiter that was histologically follicular adenoma and Category-IV (SFM) in Bethesda system.

When compared with other studies using TBSRTC with histological follow up, sensitivity and NPV of the present study were consistent with most of the studies (Table VI). The specificity and PPV were higher than most of the other studies, which may be due to small sample size in this present study.

Conclusion

By dint of its higher sensitivity, specificity, predictive values and accuracy TBSRTC has been proved to be better than  conventional system for reporting thyroid cytopathology. So, it should be useful for standardization of thyroid cytopathology reporting. However, studies needed to explore its effect in reducing inter-observer variation of reporting thyroid cytopathology as well as its usefulness to the clinicians in decision making.

 References

  1. Bagga PK, Mahajan NC. Fine needle aspiration cytology of thyroid swellings: How useful and accurate is it? Indian Journal of cancer, 2010 Oct 1;47(4):437.
  2. Hamberger B, Gharib H, Melton LJ, Goellner JR, Zinsmeister AR. Fine-needle aspiration biopsy of thyroid nodules: impact on thyroid practice and cost of care. The American journal of medicine. 1982 Sep 1;73(3):381-4.
  3. Yassa L, Cibas ES, Benson CB, Frates MC, Doubilet PM, Gawande AA et al. Long‐term assessment of a multidisciplinary approach to thyroid nodule diagnostic evaluation. Cancer Cytopathology: Interdisciplinary International Journal of the American Cancer Society. 2007 Dec 25;111(6):508-16.
  4. Mondal SK, Sinha S, Basak B, Roy DN, Sinha SK. The Bethesda system for reporting thyroid fine needle aspirates: a cytologic study with histologic follow-up.Journal of Cytology. 2013; 30(2):94.
  5. Cibas ES, Ali SZ. The Bethesda system for reporting thyroid cytopathology. Thyroid. 2009 Nov 1;19(11):1159-65.
  6. Schinstine M. Pathology Hawaii Hotline: A Brief Description of the Bethesda System for Reporting Thyroid Fine Needle Aspirates. Hawaii medical journal. 2010 Jul; 69(7):176.
  7. Wang HH. Reporting thyroid fine‐needle aspiration: literature review and a proposal. Diagnostic cytopathology. 2006 Jan; 34(1):67-76.
  8. Ali SZ and Cibas ESThe Bethesda system for reporting thyroid cytopathology: definitions, criteria and explanatory notes. Springer Science & Business Media.2010
  9. Ahmed S, Ahmad M, Khan MA, Kazi F, Noreen F, Nawaz S, Sohail I. The interobserver reproducibility of thyroid cytopathology using Bethesda Reporting System: Analysis of 200 cases. J Pak Med Assoc. 2013 Oct 1;63(10):1252-5.
  10. Bhasin TS, Mannan R, Manjari M, Mehra M, Sekhon AK, Chandey M, Sharma S, Kaur P. Reproducibility of ‘The Bethesda System for reporting Thyroid Cytopathology’: a multicenter study with review of the literature. Journal of clinical and diagnostic research: JCDR. 2013 Jun; 7(6):1051.
  11. Mufti ST, Molah R. The Bethesda system for reporting thyroid cytopathology: a five-year retrospective review of one center experience. International journal of health sciences. 2012 Jun; 6(2):159.
  12. Pathak P, Srivastava R, Singh N, Arora VK, Bhatia A. Implementation of the Bethesda System for Reporting Thyroid Cytopathology: interobserver concordance and reclassification of previously inconclusive aspirates. Diagnostic cytopathology. 2014 Nov; 42(11):944-9.
  13. Auger M, Nayar R, Khalbuss WE, Barkan GA, Benedict CC, Tambouret R et al. Implementation of the Bethesda System for Reporting Thyroid Cytopathology: observations from the 2011 thyroid supplemental questionnaire of the College of American Pathologists. Archives of Pathology and Laboratory Medicine. 2013 Nov; 137(11):1555-9.
  14. Crippa S, Dina R. Interobserver reproducibility of thyroid fine-needle aspiration using the UK Royal College of Pathologists’ classification system. American journal of clinical pathology. 2012 May 1;137(5):833-5.
  15. Mamatha M, Sekhar SC, Rani HS, Anil SS and Vandana G. A comparative study between conventional system and the Bethesda system applied for reporting thyroid cytopathology. International Archives of Integrated Medicine.2015; 2(3):87 – 95
  16. Mehra P, Verma AK. Thyroid cytopathology reporting by the Bethesda system: a two-year prospective study in an academic institution. Pathology research international. 2015;2015. 240505.doi: 1155/2015/240505
  17. Ahmed S, Ahmad M, Khan MA, Kazi F, Noreen F, Nawaz S, Sohail I. The interobserver reproducibility of thyroid cytopathology using Bethesda Reporting System: Analysis of 200 cases. J Pak Med Assoc. 2013 Oct 1; 63(10):1252-5.
  18. Bukhari MH, Khan AA, Niazi S, Arshad M, Akhtar ZM, Al-Sindi KA. Better thyroid cytopathology reporting system may increase the clinical management and patients outcome. J Cytol Histol. 2012;3(6):1000158.
  19. Hajmanoochehri F, Rabiee E. FNAC accuracy in diagnosis of thyroid neoplasms considering all diagnostic categories of the Bethesda reporting system: A single-institute experience. Journal of Cytology/Indian Academy of Cytologists. 2015 Oct; 32(4):238.
  20. Jo VY, Stelow EB, Dustin SM, Hanley KZ. Malignancy risk for fine-needle aspiration of thyroid lesions according to the Bethesda System for Reporting Thyroid Cytopathology. American journal of clinical pathology. 2010 Sep 1;134(3):450-6.
  21. Sanchez AM and Stahl RE.The Thyroid, Parathyroid, and Neck Masses Other Than Lymph Nodes.in: Koss LG, Melamed MR, editors. Koss’ diagnostic cytology and its histopathologic bases. Lippincott Williams & Wilkins; 2006.pp1148-1173.
  22. Joshi D and Jesalpura NS. Comparision Between Bethesda System and Conventional System in Thyroid Cytopathology: International Journal of Scientific Research, 2015;4(9).
  23. Naz S, Hashmi AA, Faridi N, Edhi MM, Kamal A and Khan M. Diagnostic accuracy of Bethesda system for reporting thyroid cytopathology: an institutional perspective.International archives of medicine, 2014; 7(1):46..
  24. Theoharis CG, Schofield KM, Hammers L, Udelsman R, Chhieng DC. The Bethesda thyroid fine-needle aspiration classification system: year 1 at an academic institution. Thyroid. 2009 Nov 1;19(11):1215-23.
  25. Bonzanini M, Amadori P, Morelli L, Fasanella S, Pertile R, Mattiuzzi A et al. Subclassification of the “grey zone” of thyroid cytology; a retrospective descriptive study with clinical, cytological, and histological correlation. Journal of thyroid research. 2011:251680.doi:10.4061/2011/251680.
  26. Gupta M, Gupta S, Gupta VB. Correlation of fine needle aspiration cytology with histopathology in the diagnosis of solitary thyroid nodule. Journal of thyroid research. 2010 Apr 18;2010:379051.

Histopathological Spectrum of Prostatic Lesions Evaluated in a Tertiary Hospital

Histopathological Spectrum of Prostatic Lesions Evaluated in a Tertiary Hospital

 *Sultana SS,1 Hossain S,2 Rahman A3


  1. *Dr. Sk Salowa Sultana, Assistant Professor, Department of Pathology, Ad-Din Women’s Medical College. salowasultana257@gmail.com
  2. Shahadat Hossain, Associate Professor, Department of Pathology, Ad-Din Women’s Medical College.
  3. Afiqur Rahman, Professor of Urology, Department of Urology, Ad-Din Women’s Medical College.

*For correspondence

 Abstract

Objective: To determine the age distribution of various prostatic lesions, to evaluate histopathological  pattern  of prostatic lesions  and  to analyze adenocarcinoma  of prostate according to Gleason  system.

Methods: This was a retrospective study comprising of 178 cases, carried out at the department of Pathology, Ad-din Women´s  Medical College Hospital during the  period of January 2017 to December 2019.

Results: Out of 178 cases, 159(89.32%) were diagnosed as benign lesion, nodular hyperplasia being the commonest one. Prostatic adenocarcinoma was found in 16(9%) cases, majority of which belonged to Gleasons score 7.

Conclusion: Histopathological examination of prostatic biopsy specimen is essential for diagnosis of benign and malignant lesions, to rule out the incidental carcinoma and HGPIN.

 [Journal of Histopathology and Cytopathology, 2020 Jan; 4 (1):33-37]

 Keywords: Nodular hyperplasia of prostate, prostatic carcinoma, HGPIN

Introduction

The  prostate that weights up to 20 gm in normal adult depends for its subsequent growth and differentiation on androgenic hormones.1,2  Lesions of prostate are extremely common over the age of 50 years and important cause of morbidity and mortality in male in advance age. Pathological processes affecting this organ include inflammation, benign nodular enlargement and tumor.1 The clinical incidence of the diseases is only 8% during the 4th decade  but it reaches 50% in the 5th decade and 75% in the 8th decade.2 Benign prostatic  hyperplasia(BPH) and carcinoma are increasingly frequent with advancing age.3  BPH results from hyperplasia of both stromal and epithelial cells, gradually being enlarged, compress and narrow the urethral canal and often leads to urinary obstruction. Inflammation of prostate is known as prostatitis and divided into acute, chronic and granulomatous prostatitis. Prostatic carcinoma is one of the most common malignancies affecting men, also it is the sixth leading cause of cancer death in male.4 Among the prostatic malignancies 95% is adenocarcinoma. premalignant lesion of prostatic adenocarcinoma  is known as high grade intraepithelial neoplasia (HGPIN). The objective of this study was to determine the age distribution of various prostatic lesions, to evaluate histopathological  pattern  of prostatic lesions  and  to analyze adenocarcinoma  of prostate according to Gleason  system.

Methods

The study was conducted in the Department  of Pathology, Ad-din Women´s Medical College Hospital – a  tertiary level hospital of Dhaka, Bangladesh. The study period was from January 2017 to December 2019. The data were collected retrospectively from histopathology register. A  total of 178 TURP (Transurethral resection of prostate) were evaluated. The received specimen were fixed in 10% formalin and routine paraffin processing followed by hematoxylin and eosin staining was done and the slides were examined under light microscope. The specimens were ananlyzed as type of specimen, age of the patient, histopathological  pattern and final diagnosis. The tumour were classified according to 2016 WHO classification and histological grading was done using modified Gleason´s system. Data  were analyzed using tables, figures and percentage.

 Results

A total of 178 cases were included in our study, all of which (100%) were TURP specimen.  In the present study, most of the prostatic lesions were benign(89.32%) followed by malignant (9.6%) and HPIN (1.12%) and ratio of benign and malignant lesions is 1:9, approximately.

In the present study, benign lesions were mostly found (45%) in the age group of 61-70 years  and 34% in the age group of 51-60 years,  whereas malignant lesions were common  41% in the age group of 71-80 years and 29% in the age group of 61-70 years of age. In our study, benign lesions(159) were nodular hyperplasia of prostate 130(73.03%) and nodular hyperplasia of prostate with co-existing prostatitis 29(16.3%). Out of 29 cases of prostatitis, 24 cases were chronic non specific prostatitis, 2 cases were granulomatous prostatitis and 3 cases were acute prostatitis.  In our study, 2(1.12%) cases were diagnosed as HGPIN and 17(9.6%) cases were diagnosed as malignant. Most of the malignant cases 16(9%)  were prostatic adenocarcinoma and 1(0.56%) was metastatic adenocarcinoma. In this study, 41% cases of malignant belong to 71-80 years age group and 29% cases belong to 61-70 years age group. According to Gleason score, most commonly (81.25%) found grade was grade 7, in this study.

Discussion

We enrolled a total of 178 cases in our study, all of which (100%) were TURP specimen. Bhatta S et al5 have found 88.54% specimen of TURP in their study. Screening procedure like trans-rectal ultrasound, prostate specific antigen (PSA) are still used, but biopsy remains the gold standard for final diagnosis.6 In the present study, most of the prostatic lesions were benign (89.32%) followed by malignant (9.6%) and HPIN (1.12%). These findings are similar to the studies done by Bhatta S et al,5 Bal et al,7 Jehoram  et al,8 and Bhat S et al.9 They found (89.58%), (87%), (93%) and (92.4%) cases of BPH in their study, respectively. In our study, ratio of benign and malignant lesions is 1:9, approximately.

In the present study, benign lesions were mostly found 45% in the age group of 61-70  years  and 34% in the age group of 51-60 years,  whereas malignant lesions were common  41% in the age group of 71-80 years and 29% in the age group of 61-70 years of age. These findings are in concordance with other studies.10,11,12

In our study, benign lesions(159) were nodular hyperplasia of prostate 130(73.03%) and nodular hyperplasia of prostate with co-existing prostatitis 29(16.3%). Out of 29 cases of prostatitis, 24 cases were chronic non specific prostatitis, 2 cases were granulomatous prostatitis and 3 cases were acute prostatitis.  Bhatta S et al found 24(25%) cases of prostatitis associated with nodular hyperplasia of prostate, out of which 22 cases were chronic non specific prostatis and two cases were acuteprostatis.5 Prostatic carcinoma is one of the most common malignancies affecting men. In our study, 2(1.12%) cases were diagnosed as HGPIN and 17(9.6%) cases were diagnosed as malignant. Most of the malignant cases 16(9%)  were prostatic adenocarcinoma and 1(0.56%) was metastatic adenocarcinoma. Bhatta S et. al5found 2.08% of HGPIN and 8.34% of prostatic carcinoma. Also Deshmukh BD et. al11 and Bhat S et. al9 found similar observation. In this study, 41% cases of malignant  belong to 71-80 years age group and 29% cases belong to 61-70 years age group. Bhat S et. al12  found 75% cases of malignancy diagnosed after 60 years. All the cases of prostatic adenocarcinoma were graded according to Gleason score which determine the tumour aggressiveness.In this study, most commonly 13(81.25%) found grade was grade 7. Albasri et al.13 found Gleasons score 5-7 as the commonest among 71 cases of prostatic adenocarcinoma. Bhat S et. al9 found 56.16% of adenocarcinoma with Gleason score 8-9.

 Conclusion

Histopathological  examination of prostatic lesions is essential for diagnosis and management. Prostatic lesions are common in the age group of 60-70 years. All the specimen received were TURP. Benign prostatic hyperplasia (BPH) was predominant type among all the lesions. Majority of the malignant lesions were incidental diagnosis and most of the malignant lesions were prostatic adenocarcinoma. Emphasis should be  given to identify premalignant lesions.

References

  1. Epstein JI. The lower urinary tract and male genital system. 8th rev ed. Kumar V, Abbas AK, Fausto N, Aster JC, editors. Robbins and Cotran. New Delhi: Elsevier Pathologic Basis of Disease, 2010. p993-1002.
  2. Rosai J. Male reproductive system. In: Rosai J, editor. Rosai and Ackerman’s Surgical Pathology. 10thed. New Delhi: Elsevier, 2011:1287-1333.
  3. A Josephin-2014, clinicopathological study of prostatic biopsy, ©2014journal of Clinical and Diagnostic 2014 Sep; 8(9): FC04-FC06.
  4. Chandanwale S, Jadhav PS, Anwekar SC, Kumar H, Buch AC, Chaudhari US, et al. Clinico-pathological study of benign and malignant lesions of prostate. IJPBS. 2013;3:162-178.
  5. Bhatta S, Hirachan S. Prostatic lesions: Histopathological Study in a Tertiary Care Hospital. JMMIHS. 2018;4(1):12-19.
  6. Garg M, Kaur G, Malhotra V, Garg R. Histopathological spectrum of 364 prostatic specimens including immunohistochemistry with special reference to grey zone lesions. Prostate Intl. 2013;1:146-151.
  7. Bal MS, Kanwal S, Goyal  AK, Singla N, Prostatic lesions in surgical biopsyspecimen. JK Pract 2011;16:33-4.
  8. Jehoram TA, Sitara AS, Mohammed EB. Hyperplastic , premalignant and malignant lesions of the prostate gland. Hum Pathol. 2005;36:480-5.
  9. Bhat S, Chaudhri S, Bhat P, Hatwal D. Histopathological study of prostatic Diseases in Garhwal Region. Int  J Sci stud. 2015: 3(8):136-140.
  10. Shakya G, Malla S, Shakya KN. Salient and co-morbid features in benign prostatic hyperplasia: A histopathological study of the prostate. Kathmandu Univ Med J. 2003;2:104-109.
  11. Deshmukh BD, Ramteerthakar NA, Sulhyan KR. Histopathological study of lesions of prostate- A five year study. Int J Health Sci Res. 2014;4:1-9.
  12. Yadav M, Desai H, Goswami H. Study of Various Histopathological Patterns in Prostate Biopsy. IJCRR. 2017;9(21):59-63.
  13. Albasri A, EL-Sidding A, Hussainy A, Mahrous M, Alhosaini AA, Alhujaily A. Histopathologic characterization of prostatic diseases in Madinah, Saudi Arabia. Asian Pac J Cancer prev. 2014;15:4175-9.

Histopathological Patterns of Ovarian Tumours and HER2 Expression in Epithelial Ovarian Carcinoma

Histopathological Patterns of Ovarian Tumours and HER2 Expression in Epithelial Ovarian Carcinoma

*Barua M,1  Hossain MI,2  Bini UH,3 Nasreen S,4 Ahamad MU,5 Bhattecharjee P,6 RahmanM Z7


  1. * Mitasree Barua, Lecturer, Department of Pathology, Chittagong Medical College, Chattogram, Bangladesh. mitakmc12@gmail.com
  2. Mohammad Ismail Hossain, Lecturer, Department of Pathology, Chittagong Medical College, Chattogram, Bangladesh
  3. Umme Habiba Bini, Assistant Professor, Department of Pathology, Pabna Medical College, Pabna, Bangladesh.
  4. Sayeeda Nasreen, Assistant Professor, Department of Pathology, Chittagong Medical College, Chattogram, Bangladesh.
  5. M. Sahab Uddin Ahamad, Associate Professor, Department of Pathology, Chittagong Medical College, Chattogram, Bangladesh.
  6. Pradip Bhattacharjee, Associate Professor, Department of Pathology, Chittagong Medical College, Chattogram, Bangladesh.
  7. Md. Zillur Rahman, Professor & Head, Department of Pathology, Chittagong Medical College, Chattogram, Bangladesh.

 *For correspondence

 Abstract

Background: Ovarian tumours are a heterogenous group of neoplasm of epithelial, stromal and germ cell origin. The management of which depends on the histological type of the tumour. Neoadjuvant chemotherapy is limited by toxicity and resistance. Hence targeted therapy is now being proposed to overcome these hurdle.

Objectives: To find out the histopathological patterns of ovarian tumours and to evaluate HER2 overexpression in epithelial ovarian carcinoma.

Methods: This study was carried out in the Department of Pathology, Chittagong Medical College, Chattogram, received from Department of Gynaecology and Obstetrics, Chittagong Medical College Hospital, Chattogram during the period from January 2016 to December 2016. A total of 92 cases of ovarian tumours were selected consecutively. The age range was 12-80 years. Histopathological sections were stained with Hematoxylin and Eosin stain and epithelial ovarian carcinoma were subjected to HER2/neu immunohistochemical stain. Histopathological patterns of ovarian neoplasm, histopathological subtyping and grading of epithelial ovarian tumours and the expression of HER2/neu among epithelial ovarian carcinomas on immunohistochemistry was analyzed.

Results: Out of total 92 cases, histopathological diagnosis showed 65 (70.7%) were benign tumours and 27 (29.3%) were malignant tumours. Histologically, surface epithelial tumours were the most common (74%) followed by germ cell tumours (21.7%) and sex cord stromal tumours (4.3%). Age incidence of benign tumour was age group of 21-40 yrs and malignant 41-60 years. One in 23 epithelial ovarian carcinoma cases (4.3%) exhibits HER2 overexpression. Only one HER2 positive case was mucinous cystadenocarcinoma grade II.

Conclusion: Surface epithelial tumours were most common followed by germ cell tumours. Serous cystadenocarcinoma were most common epithelial ovarian carcinoma.


[Journal of Histopathology and Cytopathology, 2020 Jan; 4 (1):23-32]

 Keywords: Ovarian tumour, Epithelial Carcinoma, HER2/neu.


Introduction

Ovarian tumours account for 3% of all cancers in females, being the second most common cancer of the female genital tract, next only to uterine cancer.1 Ovarian cancer, traditionally known as the silent killer, is a dreaded disease because of its vague, nonspecific symptoms and late presentation. Worldwide, it is the seventh most common cause of cancer and eighth most common cause of cancer-related death among women.2 It is be a disease of developed and industrialized countries where parity of women is low. As the standard of living increases and resources for a medical infrastructure improve in Bangladesh, there will be an increased need to address less common but highly lethal cancers such as ovarian cancer. Globocan predicts a change in the reported incidence of ovarian cancer from 2912 in year 2012 to 3132 in year 2015.3

Risk factors for ovarian cancer are not well defined. However, there is general agreement on two: nulliparity and family history. Women 40 to 59 years of age who have taken oral contraceptives or undergone tubal ligation have a reduced risk of developing ovarian cancer.4 Two treatment options, available for ovarian cancers in advanced stage, are either a primary surgical cytoreduction/debulking or chemotherapy in an attempt to downstage the tumor followed by surgery. Though platinum-based therapy has produced an impressive result, chemoresistance and toxicity are creating hurdles. To overcome this, monoclonal antibodies targeting HER2/neu, a transmembrane protein homologous to epidermal growth factor receptor, has been introduced recently that might bring a new era of management.5

HER2/neu protein expression is commonly measured using immunohistochemistry (IHC).6 Overexpression of HER2/neu is seen in 20–30% patients with ovarian cancer. Some of these differences are likely to be attributable to the diagnostic technique used to measure HER2 expression. HER2/neu overexpression in epithelial ovarian carcinomas has not been studied as extensively as it has been studied in case of breast carcinomas, especially in Bangladesh scenario.

The aim of my study was to determine histopathological patterns of ovarian tumor and to evaluate the frequency of the expression of HER2 among epithelial ovarian carcinomas.

 Methods

It was a cross-sectional descriptive study carried out in the Department of Pathology of Chittagong Medical College, Chattogram, Bangladesh. Study period was for one year from 1st January, 2016 to 31st December, 2016. All female patients clinically diagnosed as ovarian neoplasm received at the Department of Pathology of Chittagong Medical College, Chattogram referred from Department of Gynaecology and Obstetrics, Chittagong Medical College Hospital (CMCH) during the specified time duration. Finally, 92 consecutive patients were selected according to time frame.

 Inclusion criteria

Patient with clinically diagnosed as ovarian tumours who underwent intervention like diagnostic laparoscopy or laparotomy; at least for biopsy in Chittagong Medical College Hospital, Chattogram.  Patient with histopathologically diagnosed ovarian tumour in the Department of Pathology, Chittagong Medical College.

 Exclusion criteria

Previously diagnosed case of ovarian tumour who already has got treatment. Patient unwilling to give written consent.

Protocol was ethically reviewed and approved by the Ethical review Committee of Chittagong Medical College, Chattogram. All the patients included in the study were informed and explained about the nature of study. Informed written consent was taken from all the subjects after full explanation of nature, purpose and potential risks of all the procedures.

A brief clinical history was taken from each patient with particular reference to the age, occupation, marital history, parity, menstrual history, family history, history of breast feeding, use of contraceptives etc. Clinical history, questionnaire, thorough physical examination, and relevant investigations were recorded in details in all cases.Routine histopathology with H & E stain and Immunohistochemistry for ovarian carcinoma were done.

H&E stained slides were examined under light microscope to get a definitive diagnosis of the ovarian tumour and its type. Histological classification was based on the 2003 World Health Organization classification of ovarian tumours. The Shimizu-Silverberg three-grade histological grading system was used in epithelial ovarian carcinoma (EOC).

The most representative tumor tissue was chosen from each epithelial ovarian carcinoma case and 4 μm sections were taken to poly-L-lysine coated slides for immunohistochemical staining. For immunohistochemistry, epitope retrieval was done with a polymer-based detection system (Envision; Dako) using a Herceptin kit (HercepTest; Dako) according to the manufacturer’s instructions.Antigen retrieval for HER2 using Hercep Test was performed by immersing and incubating the slides in 10 mmol/L citrate buffer in calibrated water bath (95- 99°C) for 40 minutes. After decanting the epitope-retrieval solution, the sections was rinsed in the wash buffer and later, soaked in the buffer for 5 to 20 minutes before staining. Then the slides were rinsed, placed in 200 μL peroxidase-blocking reagent for 5 minutes, rinsed, placed in 200 μL primary anti-HER2 protein (or negative control reagent) for 30 minutes, rinsed twice, and finally immersed in 200 μL substrate chromogen solution (3,3´-diaminobenzidinetetrahydrochloride, DAB) for 10 minutes. The slides were counter stained with hematoxylin and finally were cover slipped.

 Results

In this study the age range of 92 ovarian tumours was 12-80 years, were divided into seven age groups and it was observed that maximum number of benign lesions 19 (20.6%) were in age groups 21-30 years. Maximum number of malignant tumours were found 9 (9.8%) in age group 41-50 years. Among 92 ovarian lesions, 68 (74%) were surface epithelial tumour, 20 (21.7%) were germ cell tumour, 4 (4.3%) were sex cord stromal tumours .

Discussion 

Current study was carried out in Departmant of pathology, Chittagong Medical College to see the histopathological patterns of ovarian tumours and HER2 expression in epithelial ovarian carcinoma (EOC).Total number of the patients in this study was 92. The age range was 12-80 years. The mean age was 34.64 years. Patients were divided into seven groups consisting of each decade as a single group and maximum number patients 23 (25%) were in 21 – 30 years group, followed by 21 (22.8%) were in 41-50 years age group. Study done in Nepal by Vaidya et al.(2014) showed highest number of patients (58%) were in 21-40 years age group which is similar to present study.7 In this study in 21-40 years age group total number of patients were 42 (45.65%). Study done in India by Bhagyalakshmi et al (2014)) patients age ranged from 11-70 years, majority of benign cases and malignant cases were between 21 to 40 years and 41 to 60 years respectively.8 Agrawal et al. (2015) also showed age ranged from 12 to 80 years with most common benign and malignant lesions cases were 21 to 40 years and 41 to 60 years respectively which was consistent with this study.9

In this study, among 92 cases, 72 (78.3%) were married and 20 (21.7%) cases were unmarried women. This is probably due to more married women presented to the outpatient department than unmarried ones. Among 72 married women 08 (11.1%) were nulliparous, 03(4.2%) were primiparous and 64 (84.7%) were multiparous.Study done in Dhaka by Dhar et al (2015) showed 8% were unmarried and 92% were married, of whom 12% were nulliparous and 80% was parous.10

Regarding socio-economic status 68 (73.9%) cases were from average socioeconomic condition, 23 (25%) were from poor and only 1 (1.1%) cases from high socioeconomic family. Among the malignant cases maximum 13 (48.1%) cases were from average socioeconomic condition. This is similar to the finding of  Dhar et al (2015).10This may be due to the fact that patients attended at a government hospital and most of the people of average and poor socioeconomic conditions usually come here to get treatment.

In this study, it was seen that, 19 (20.7%) had history of hormonal contraceptive use and 49 (53.3%) had no history. Among 27 malignant cases 3 (11.1%) had history of contraceptive use. Ness et al (2011) had reported that oral contraceptives reduce the risk of developing ovarian cancer.11

In this study 75 (81.5%) patients presented with lower abdominal pain 74 (80.4%) with lower abdominal mass. Study done by Jaffar et al (2013) showed, abdominal pain was in 90% cases, abdominal mass was present in 24% of the patients with benign tumours and in 66% with malignant tumours.12

In the present study, among 65 benign lesions 20 (21.7%) cases had increased level of CA-125 and among 27 malignant lesions 3(3.3%) cases were found within normal level.Miralles et al. (2003) suggested that variety of malignancies and benign conditions courses with increased CA-125 level and it is observed that CA-125 is very important as tumour marker for malignancy.13

In the present study, out of 65 benign tumours 62(95.3%) were unilateral and 3(4.6%) were bilateral. Out of 27 malignant tumours 5(18.51%) were bilateral and 22(81.48%) were unilateral. Modepalli et al (2016) reported 93.8% of the neoplasms were unilateral and remaining 6.2% of the lesions were bilateral.14 Benign tumours were more unilateral than malignant tumours. In this present study, out of 92 cases, maximum number of lesions were 48 (52.2%) in the right side of abdomen which is similar to the study done by Modepalli et al (2016).14

Among 92 cases 43 (46.7%) were solid and cystic lesion, 41 (44.6%) were cystic lesions and 8 (8.7%) were solid. Similar study done by Agrawal et al (2017) showed 83.3% benign tumours were cystic whereas 65.3% malignant tumours were solid and cystic.9 Benign tumors were more often cystic in consistency in this study and malignant tumors were solid consistency which was comparable to the study of Kanthikar et al. (2014).15

In this study of the 92 cases of ovarian tumours, 67 (70.7%) were benign and 27 (29.3%) were malignant. Similar studies in India carried out by GG swamy et al. (2010) showed 86 (71.6%) benign tumours, 30 (25.1%) malignant and 4 (3.3%) borderline tumors.16 In Nepal R Jha et al reported 83.9% benign, 16.1% malignant and 2.8% borderilne ovarian tumour.17 In  Pakistan a similar study by Ahmed et al showed 59.18% benign and 40.81% malignant tumour. In this study there was no borderline malignancy which were similar to the study done by Yasmine et al. (2008).18

Among the histologic types, in the present study, surface epithelial tumours were most common 68 (74%), germ cell tumour was 20 (21.7%), and sex cord stromal tumour was 4 (4.3%).Similar observation made by Pilli et al.(2002) showed 70.9% surface epithelial tumours, 21.2% germ cell tumours and 6.7% sex cord stromal tumours.19

In this present study Among 92 cases the most common benign surface epithelial tumour was mucinous cystadenoma 26 (28.3%) followed by serous cyst adenoma 18 (19.6%) and benign brenner tumour 1(1.1%). The most common benign germ cell tumour was mature cystic teratoma 18 (19.6%).In this study benign sexcord stromal tumour was fibroma 2(2.2%). Studies done by Bhagyalakshmi et al (2014)8 and Mondol et al (2011)20 showed serous cystadenoma was the most common benign tumour. Study done by Ahmed et al (2000) however found the most common benign tumour to be benign cystic teratoma.21

The commonest malignant tumour was serous cyst adenocarcinoma 13 (14.1%), followed by mucinous cystadenocarcinoma 8 (8.7%), malignant brenner tumour 1 (1.1%) and clear cell carcinoma 1 (1.1%). Similar results were shown in studies by Mondol et al (2011) and Yogambal et al (2014).22

In this present study 23 cases of epithelial ovarian carcinoma (EOC) were evaluated for HER2/neu protein expression using immunohistochemistry.The positive expression rate of HER2/neu in this study was 1(4.3%).This is comparable to the rate of  HER2/neu positivity in EOC reported in the literature,which ranges from 7-50%Verri et al (2005),23 Berchuck et al (1990),24 Mayr et al (2006).25 The variation in HER2/neu protein expression rate in different studies may be early stage and 17% of patients with advanced stage disease in the study by Kacinsky et al (1992). However, multiple factor may be involved in producing a wide range of positivity, such as sample size, the detection technique and type of monoclonal antibody used, staining intensity and the tissue where analysis is performed. Studies with populations smaller than 100 patients reported a frequency of 1.8-76%,(Serrano-Olvera et al., 2006).26

In this study among 8 mucinous cystadenocarcinoma, HER2 expression was positive in 1 (12.5%) case and was in Grade-II. In the study done by Missaoui et al (2014),27 HER2 expression was described in 14.3% of mucinous carcinoma. Study in Nijeria done by Ajani et al.(2015) 28 observed that a higher proportion of serous carcinoma (as opposed to mucinous carcinoma) was HER2/neu positive. Sarkar et al (2015)2 also showed that HER2 expression was more intense for high grade serous carcinoma.

In this study HER2 expression is relatively common in mucinous epithelial carcinoma of the ovary and trastuzumab therapy would be an option for patients with mucinous carcinoma when the tumour has HER2 overexpression.

The study also has some limitations. This study was severely constrained by the limited duration that led to have small population size and this study was done in patient who underwent surgery and samples were collected from Chittagong Medical College and Hospital only. In spite of these reason the present study showed more or less acceptable findings with consideration of the observations by others.

 Conclusion

Ovarian cancer presents a tremendous clinical challenge to gynecologists, medical oncologists and radiotherapists. It is a silent menace and is not associated with significant symptoms. Surface Epithelial Tumours were the commonest group followed by Germ Cell Tumours. Most common Germ cell tumours were mature cystic teratoma occured in much younger women. Malignant ovarian neoplasms were more common in patients above 40 years. Sex Cord Stromal Tumours were also common with Fibroma and Granulosa cell tumour. Unilateral involvement of ovarian neoplasms was more common than bilateral and involvement of right ovary was more than the left. Mucinous cystadenoma was the commonest benign ovarian neoplasm while the commonest malignant tumour was serous cystadenocarcinoma. Mucinous epithelial carcinoma have expressed HER2.

 References

  1. Lora EH, & Edyta PC. The Female Genital Tract. 8 ed. Philadelphia; Saunders; 2010.1040p.
  2. SarkarM, JhaT, Das TK, SauV et al. Spectrum of Epithelial ovarian tumors with HER2/new expression by the carcinomas among patients admitted in a tertiary care hospital in Eastern India.J Med Sci Public Health. 2015; 4(10):1388-1392.
  3. Pervin S, Islam F, Hall T, & Goodman A. The management of ovarian cancer in Bangladesh: A report of a long-term survivor.Austin Journal of obstetrics and Gynecology. 2015;2(4):1047.
  4. Ness RB, Dodge RC, Edwards RP, et al. Contraception Methods, beyond Oral Contraceptives and Tubal. Ann Epidemiology. 2001;21(3):188–196.
  5. Ray-Coquard I, Gaustalla JP, Allouache D, Combe M, et al. HER2 Overexpression / amplification and trastuzumab treatment in advanced ovarian cancer: a GINECO Phase II study. Clin Ovarian Cancer. 2008;1(1):54-59.
  6. Wolff AC, Hammond ME, Schwartz JN. et al. American Society of Clinical Oncology/College of American Pathologists guideline recommendations for human epidermal growth factor receptor 2 testing in breast cancer. J Clin Oncol. 2007;25:118–45.
  7. Vaidya S, Sharma P, KC S,Vaidya SA . Spectrum of ovarian tumour in a referral hospital in Nepal. Journal of Pathology Nepal. 2014; l4: 539-543.
  8. BhagyalakshmiA, SreelekhaA, Sridevi S, Chandralekha J, Parvathi G,Venkatalaksmi A Prospective study of histopathological patterns of ovarian tumours in a tertiary care centre. International Journal of Research in Medical Sciences. 2014;2(2):448-456.
  9. Agrawal P, Kulkarni DG, Chakrabarti PR, Chourasia S, Dixit M, Gupta K. Clinicipathological Spectrum of Ovarian Tumors: A 5 Year Experience in a Tertiary Health Care Center. Journal of Basic and Clinical Reproductive Science. 2015;4(2), 90-96.
  10. Dhar SR, Begum S, Zabin F, Akter S. Socio-demographic Characteristics of Ovarian Tumor Patients attended at a tertiary care hospital in Dhaka city. Journal of Current and Advance Medical Research. 2015;2(2):39-41.
  11. Ness RB, Dodge RC, Edwards RP, et al. Contraception Methods, beyond Oral Contraceptives and Tubal. Ann Epidemiology. 2001;21(3):188–196.
  12. Jaffer Y, Ehsan N, Ambreen. Clinical presentation of ovarian tumors. Journal of Surgery Pakistan (International). 2013;18(2):82-86.
  13. Miralles C, Orea M, España P, Provencio M, Sánchez,A, Cantos B,etal.Cancer Antigen 125 Associated With Multiple Benign and Malignant Pathologies. Annals of Surgical Oncology. 2003;10(2):150–154 DOI: 10.1245/ASO.2003.05.015
  14. Modepalli N and VenugopalSB. Clinicopathological Study of Surface Epithelial Tumours of the Ovary. An Institutional Study,Journal of Clinical and Diagnostic Research. 2016;10(10):01-04.
  15. Kanthikar SN,Dravid NV, DeorePN ,Nikumbh DB, Suryawanshi KH. et al.Clinico-Histopathological Analysis of Neoplastic and Non-Neoplastic Lesions of the Ovary: A 3-Year Prospective Study in Dhule, North Maharashtra, India,Journal of Clinical and Diagnostic Research. 2014;8(8):04-07.
  16. Swamy GG, SatyanarayanaN.Clinicopathological analysis of ovarian tumor – a study on five year samples. Nepal Med Coll J. 2010;12(4):221-3.
  17. Jha R & Karki S. Histological pattern of ovarian tumors and their age distribution.Nepal Med Coll J. 2008;10(2):81-85.
  18. Yasmin S, Yasmin A, Asif M. Clinicohistological pattern of ovarian tumors in Peshawar region. J Ayub Med Coll Abbottabad. 2008;20:11–13.
  19. Pilli GS, Suneeta KP, Dhaded AV, Yenni VV. Ovarian tumours: A study of 282 cases. J Indian Med Assoc. 2002; 100:423-424.
  20. Mondal SK, Bandopadhyay R, Nag DR, Roychowdhury S, Mondal PK, Sinha SK, Histological pattern, bilaterality and clinical evaluation of 957 ovarian neoplasms. A 10 year study in a tertiary hospital of Eastern India. J Can Res Ther.2011; 7:433-437.
  21. Ahmad Z, Kayani N, Hasan SH & Muzaffar S. Histopathological Pattern of Ovarian NeoplasmJ Pak Med Assoc. 2000;50(12):416-419.
  22. Yogambal M, Arunlatha P, Chandramouleeswari K, PalaniappanV.Ovarian tumors- incidence and distribution in a tertiary referral center in south India. IOSR-JDMS 2014;13(2):74-80.
  23. Verri E, Guglielmini P, Puntoni M, Perdelli L, Papadia A, Lorenzi P, et al. HER2/neuoncoprotein overexpression in epithelial ovarian cancer: evaluation of its prevalence and prognostic significance. Oncology. 2005;68:154–61.
  24. Berchuck A,Kamel A,Whitaker R, Kerns B, Olt G, Kinney R, et al. Over-expression of HER-2/neu is associated with poor survival in advanced epithelial ovarian cancer.Cancer Res.1990;50:4087–91.
  25. Mayr D, Kanitz V, Amann G, et al. HER-2/neu gene amplification in ovarian tumours: a comprehensive immunohistochemical and FISH analysis on tissue microarrays. Histopathology. 2006;48:149–56.
  26. Serrano-OlveraA,Dueñas-González A, Gallardo-Rincón D, Candelaria M, Garza J. et al . Prognostic, predictive and therapeutic implications of HER2 in invasive epithelial ovarian cancer. Cancer treatment reviews. 2006;32(3):180-90.
  27. Missaoui N, Ben AS, Ayachi M, Hmissa S,  Yaacoubi M et al. (2014). HER2 Expression in Ovarian Mucinous Carcinomas in Tunisia. Asian Pacific journal of cancer prevention: APJCP. 2014; 15(19): 8121-5.
  28. Ajania MA, Salamia A, Awoludeb OA,Oluwasolaa AO, and Akang EU, etal. The expression status of human epidermal growth factor receptor 2 in epithelial ovarian cancer in Ibadan, Nigeria South Afr J Gynaecol Oncol. 2016; 8(1):1–13.