jhc-2019-v-3-n-2-Is-histopathological-kabir-an

Review Article

Is Histopathological  Examination Essential  for the Diagnosis of Psoriasiform Dermatitis?

*Kabir AN,1 Rahman MM 2

  1. *Dr. AKM Nurul Kabir, Associate Professor, Department of Pathology, Bangabandhu Sheikh Mujib Medical University, Dhaka, Bangladesh. kabir56@gmail.com
  2. Mohammad Mosiur Rahman,  Assistant Professor, Department of Pathology, Bangabandhu Sheikh Mujib Medical University, Dhaka, Bangladesh

 *For correspondence

Abstract

Psoriasiform dermatitis encompasses a wide range of diseases, some of which show both clinical and histological overlap. Psoriasis is generally thought to be a genetic disease that is triggered by environmental factors. Psoriasis is characterized by an abnormally excessive and rapid growth of the epidermal layer of the skin.  Abnormal production and an over abundance of skin cells result from the sequence of pathological events in psoriasis, can be shown as a higher Ki-67 index compared with normal appearing, non-lesional skin. Morphometric analysis  of  histological features can also give a quantitative dimension  to histopathology  in diagnosis of psoriasis and in differentiating from other psoriasiform dermatitis. Psoriasis is also regarded as a T-cell mediated disorder, mainly CD4+ (helper/inducer) lymphocytes along with CD8+ subsets are known to occur.  The patient often prove to be a diagnostic dilemma for both dermatologists and pathologists alike. However, clinical features when considered alone may not be reliable, as they vary with both disease duration and treatment.  Though to give a precise diagnosis one relies on clinical correlation, histopathology is essential as it is possible to assign specific diagnosis in most cases with a logical and systematic histopathological approach. Morphometry along with the help of Ki-67 & Cyclin D1 and other immunostains of keratinocytes, and immunophenotyping of T-cell infiltrate, a definitive diagnosis can be made.

 [Journal of Histopathology and Cytopathology, 2019 Jul; 3 (2):151-161]

Key words: Psoriasis, Psoriasiform dermatitis, Morphometry, Ki-67, CD4+, CD8+

 Introduction

Psoriasiform  dermatitis  encompasses a wide range of inflammatory dermatoses, some of which show both clinical and histological overlap.  The term psoriasiform means  that  the lesion either clinically or histopathologically mimic  psoriasis and this group includes: psoriasis- the prototype of psoriasiform dermatitis,1 and others as  seborrheic dermatitis,  pityriasis rubra pilaris (PRP), allergic dermatitis, atopic dermatitis , nummular dermatitis,  lichen simplex chronicus (LSC), prurigo nodularis,  pityriasis rosea (PR), inflammatory linear verrucous  epidermal nevus (ILVEN) and mycosis fungoides (MF). Besides, clinical features in one patient may differ at different times and the diagnosis get obscured.3 As there is varied clinical presentation, a definitive histopathological  diagnosis is essential in the treatment of such inflammatory dermatoses.1 It is a challenging  task even to experienced pathologists to give a precise diagnosis every time and one relies also on clinical correlation. However, a stepwise systematic histopathological approach enables one to reach at a specific diagnosis in most cases.2

The morphometry parameters such as length of rete ridges, the length of dermal papillae and the ratio of length/average width of rete redges are statistically significant in the differentiating  psoriasis from psoriasiform dermatitis and can be used in addition to routine histopathology.3 As the prototype of psoriasiform dermatitis, psoriasis is a hyperproliferative skin disorder with increased epidermal turnover rate and mitotic index, proliferation markers Ki-67 & Cyclin D1 immunostain of keratinocytes can be added as diagnostic tools  to differentiate from other non- psoriasiform dermatitis.4  Expression levels of pRb and p53 were found to be higher in the psoriasis group in a study,  compared with the normal epidermis.5  Psoriasis is an autoimmune skin disease and regarded to be T- cell mediated disorder. CD4+ T-cells are important in initiating and maintaining the pathogenic process of psoriasis but cross-primed CD8+ T-cells are the main effector cells. Mixtures of CD4+ T cells and CD8+ T-cells are found in papillary dermis and epidermis of psoriatic lesion.  Psoriasiform lesions on the other hand show a high proportion of CD4+ T-cells in dermis.  Immunophenotyping of T-cell infiltrate in the lesion can be done in differentiating the cases.6


History of Psoriasis

History of psoriasis begins in Ancient Greece, when psoriasis, leprosy, and other inflammatory skin disorders were believed to be the same condition and the Greeks termed the skin diseases as  psora, lepra and lichen. Psora referred to itch, and lepra from lopos & lepo (the epidermis & to scale respectively). Hippocrates (460-377 BC) used the word lopoi to describe the dry, scaly, disfiguring disorders.  The Old Testament also lumped together many cutaneous   disorders, including leprosy and psoriasis, by the biblical term tsaraat or zaraath. Lepers were considered divinely punished, and cruelty was imposed upon those who were suffered from psoriasis and leprosy alike. Roman medical writer Celsus (25BC-45AD) first described papulosquamous diseases, suggesting as psoriasis one of these. Galen (133-200) first used the term psoriasis, but his description was likely represented seborrheic dermatitis. Gilbert (1797-1866) and Hebra finally distinguished the clinical picture of psoriasis from that of leprosy.7

 Epidemiology

Although psoriasis occurs worldwide, it is a common chronic inflammatory skin disorders affecting 1.5-2% population in the western countries and 1.3% in general population.6 The prevalence of psoriasis is low in certain ethnic groups such as the Japanese.8

Psoriasis can present at any age and has been reported at birth and in older people of advanced age. A bimodal age of onset has been recognized in several large studies. The mean age of onset for the first presentation of psoriasis can range from 15 to 20 years of age, with a second peak occurring at 55–60 years. Henseler and Christophers studied a series of 2147 patients and also reported as two clinical presentations of psoriasis, type I and II. Type 1 begins on or before age 40 years; Type II begins after the age of 40 years. Type I disease accounts for more than 75% of cases. Patients with early onset, tended to have more relatives affected and more severe disease than patients who have type II psoriasis. In addition, strong associations have been reported with human leukocyte antigen (HLA)-Cw6 in patients with early onset of psoriasis. The course and progress of psoriasis is unpredictable. In one study, 39% of patients reported complete remission of disease at the age between one and 54 years. Higher figures have been reported in Japan.8 A family history of the disease is common. Approximately 30% of patients have a first-degree relative with psoriasis, and the risk of psoriasis increases with the number of affected relatives a patient has.9

 Lifestyle and Morbidity

There is a link between cigarette smoking and psoriasis severity. There is sufficient evidence that aggravation of psoriasis is associated with alcohol consumption. Various recent studies report association of diabetes and other cardiovascular diseases to the severe form of psoriasis.10 Recent research suggests that patients with psoriasis have a systemic inflamma­tory state, putting them at increased risk of cardiovascular complications, including metabolic syndrome, peripheral vascular disease, stroke, myocardial infarction, and cardiac death.11  Psoriasis is increasingly being recognized as a disease that not only affects the skin but also has multi-systemic implications. Increasing epidemiological evidence suggests that patients with psoriasis may be more obese compared with the general population. Although the exact mechanism underlying the epidemiological association between psoriasis and obesity is uncertain, researchers have theorized that adipocyte elaboration of pro-inflammatory cytokines may exacerbate psoriasis.12 Many, but not all, studies have shown a positive association between metabolic syndrome and cardiovascular disease (CVD) and psoriasis, especially for (young) patients with moderate to severe disease. A recent study showed that Glyc A, which is a novel biomarker for systemic inflammation  was associated with psoriasis.13  Nearly 60% of psoriasis patients and 40% of psoriatic arthritis patients report their disease as a large problem in their everyday life. Psychosocial limitations of both diseases include enduring low self-esteem, feeling physically unattractive or sexually undesirable and avoiding social activities.14

Etiology

Etiology of psoriasis remains unknowneven though, it is believed to be multifactorial with numerous key components including genetic susceptibility, environmental triggers in combination with skin barrier disruption and immune dysfunction.15 Various data suggest that infection is an important trigger for psoriasis. Streptococcal throat infection can initiate and exacerbate chronic psoriasis.15 Another research has shown that the composition of the cutaneous microbiota is related to many dermatological diseases including  psoriasis, atopic dermatitis, and acne vulgaris.16

Genetic Factors

Epidemiological studies have demonstrated that psoriasis has an important genetic component, where the role of environmental triggers (e.g., stress, mechanical trauma and streptococcal infections) is well documented.  Familial recurrence is also documented and disease concordance is higher in monozygotic than dizygotic twins. So, psoriasis is widely regarded as a multifactorial disorder caused by the interaction between inherited susceptibility alleles and environmental risk factors.17 The molecular genetic basis of psoriasis is complex, however, there are evidence that multiple genes are involved. Seven major psoriasis susceptibility loci have been reported and   a major susceptibility locus for psoriasis is at 6p21, referred to as PSORS1 and is overrepresented in all populations tested.  An association between psoriasis and other loci has also been reported on chromosomes 1p (PSORS7), 1q (PSORS4), 3q (PSORS5), 4q (PSORS3), 17q (PSORS2), and 19p (PSORS6). The strength of associations between such genes and susceptibility to psoriasis, apart from PSORS1, is variable, may relate, in part, to heterogeneity among different populations.8

 Mechanism

Psoriasis is characterized by an abnormally excessive and rapid growth of the epidermal layer of the skin. Abnormal production of skin cells and an overabundance of skin cells result from the sequence of pathological events in psoriasis.  Skin cells are replaced every 7 days in psoriasis rather than the usual about 53 days.18 Exclusive cellular “responsibility” for the induc­tion and maintenance of psoriatic plaques has not been clearly defined. Increased proliferation of keratinocytes and endothelial cells in conjunction with APC/T cell/monocyte/macrophage inflammation leads to the distinct epidermal and vascular hyperplasia that is characteristic of lesional psoriatic skin.15  CD8+ T cells seem to be dominant in the epidermis whereas the CD4 + T cells predominant subset in the dermis.  Activated CD4+ T cells produce a variety of  cytokines  including interleukin-2 (IL-2), TNFα and γINF.  TNFα stimulating keratinocytes may produce  IL -8, a potent T- lymphocyte and neutrophil chemoattractant  and may involved in the formation of Munro microabscess. γINF is believed to play in important role in the initiation of psoriatic lesion.18 In individuals with a genetic predisposition, external stimuli such as trauma (known as Koebner phenomenon), infections, stress, drugs, and alcohol can all trigger an initial episode of psoriasis. This initial trigger activates the innate immune system (Figure 1). Complexes of the antimicrobial peptide LL-37 and host DNA/RNA, both released by keratinocytes after common epidermal damage, activate plasmacytoid dendritic cells (pDCs) to produce large amounts of type I IFNs (α/β).  Subsequently, type I IFNs trigger maturation and differentiation of dermal dendritic cells (dDCs), and these dDCs then stimulate autoreactive T cells. Thereby, psoriatic autoimmune T cells are biased to produce Th1 and Th17/Th22 cells and which induce TNFα,/INFγ and IL-17/IL-22 production respectively. These mediators act on keratinocytes, leading to the activation and proliferation. In addition, type I IFNs directly upregulate IL-22 receptor (IL-22R) on keratinocytes, increasing their responsiveness to IL-22, and inhibits terminal differentiation and induces hyperproliferation of keratinocytes leading to epidermal hyperplasia, resulting psoriasis.19  In psoriasis , along with epidermal changes there is markedly increased dermal vascularity. The dermal vascular changes have been evaluated and shown to be due to change from arterial-type vessels to venules. The vascular changes may also precede the epidermal alterations, as shown in some studies.20

Clinical Features

Psoriasis is a papulosquamous disease with variable morphology, distribution, severity and course. Papulosquamous diseases are characterized by scaling papules and plaques.8  There are five clinical subtypes of psoriasis: vulgaris (plaque), guttate, pustular, inverse, and erythrodermic. The most common variant of psoriasis is plaque psoriasis, which includes approximately 85%–90% of psoriatic patients.15 The lesions are typically distributed symmetrically on the extensor surfaces of elbows, knees, and lumbosacral area and scalp. Psoriasis may also develop at the site of trauma, known as Koebner’s phenomenon.  Guttate psoriasis has drop-shaped lesions.  Inverse psoriasis forms red patches in skin folds. Pustular psoriasis presents as small non-infectious pus-filled blisters. Erythrodermic psoriasis involves widespread inflammation and exfoliation of the skin over most of the body surface. Psoriatic nail disease affects fingernails more commonly than toenails with small pits in the nail plate.8

Clinical Diagnosis

Psoriasis is a clinical diagnosis, and a skin biopsy is usually not necessary for a classic presentation of the disease.9 Diagnosis of psoriasis is usually based on the appearance of the skin. The characteristic lesions are sharply demarcated, scaly, erythematous plaques, papules, or patches on skin that may be pruritic and/or painful. They may be ovoid, round or irregular and often distributed symmetrically.9 Auspitz sign, named after Heinrich Auspitz, where there is pinpoint bleeding on removal of scales from the lesions of psoriasis. The test by which Auspitz sign is elicited by light tangential scratching with the edge of glass slide is called as Grattage test can be used  as clinical tool.21

Microscopic Diagnosis

Histopathology is considered as a “gold standard” for the diagnosis of most dermatological conditions including psoriasis.21 Common histological features in  psoriasis vulgaris are  hyperkeratosis, parakeratosis,  psoriasiform hyperplasia (Figure 2),  Munro microabscess / spongioform pustule of Kogoj,   thin suprapapillary plate, hypogranulosis, dilated capillaries in papillary dermis and dermal inflammation.1  However, other than  Munro microabscess, spongioform pustule of Kogoj and dilated tortuous capillaries in papillary dermis,  the remaining features , such as  parakeratosis,  psoriasiform hyperplasia can be seen  also in chronic eczematous dermatitis, such as atopic dermatitis, nummular dermatitis or allergic contact dermatitis and appear to be “psoriasiform”.18  However, following a systematic approach one can reach at conclusive diagnosis.


Tirumalae described a detail  microscopic description for definitive diagnosis as follows.2

 Scanning magnification

Examination of microscopic sections under scanning magnification forms the first step. The presence of evenly elongated, thin rete ridges with equally long dermal papillae can seen in one condition i.e., psoriasis. All other diseases exhibit an uneven psoriasiform pattern, where rete ridges are of uneven of lengths and thickness with thick supra-papillary plates as in PRP (Figure 3).

 Stratum corneum

The normal basket-weave pattern is lost in most cases and it is common to find parakeratosis. Parakeratosis can be present in small mounds or may be broad and confluent.  Mounds of parakeratosis can be present throughout the epidermis in conditions like psoriasis and dermatophytosis, in seborrheic dermatitis confined to the infundibular ostia or seen in both locations in PRP.  The classic “checkerboard” pattern i.e., parakeratosis staggered in both vertical and horizontal fronts is seen in PRP. Confluent parakeratosis is seen in dermatophytosis, syphilis, pityriasis lichenoides chronica (PLC) and most importantly, in MF. A sharply defined thick zone of parakeratosis alternating with orthokeratosis and mild papillomatosis are features of ILVEN.

Epidermis

Diminished or absent granular layer is seen in classic psoriasis, but is not a constant feature. Significant amounts of plasma in the scale crust goes against a diagnosis of psoriasis, and  large amounts of plasma and a rapidly proliferating epidermis are hostile to fungi. The finding of spongiotic vesicles in a psoriasiform dermatitis are seen in allergic contact/nummular dermatitis and seborrheic dermatitis. Spongiotic psoriasiform pattern is also encountered in patch-stage of MF.

 Changes in Papillary Dermis

Psoriasis is characterized by thin supra-papillary plates and elongated dermal papillae with dilated, tortuous capillaries. The presence of extravasated erythrocytes is a sign of acuteness and is seen in eruptive psoriasis and PR. Vertical streaks of collagen with uneven psoriasiform acanthosis and compact orthokeratosis is diagnostic of LSC. However, changes of LSC can be superimposed on any chronic, itchy dermatitis including psoriasis. In contrast, thin haphazard, wiry bundles of collagen are seen in the papillary dermis in PLC and MF.

 Nature of Infiltrate

Most of the psoriasiform dermatoses are dominated by lymphocytes in the dermis. When eosinophils are present among them, it indicates allergic/contact dermatitis or a drug eruption.  However, eosinophils are not a pre-requisite for diagnosis of either of these conditions. Histiocytes and plasma cells in a psoriasiform dermatitis with scale crusts give hints for secondary syphilis. Superficial and deep infiltrates are seen in syphilis and lichen striatus (LS).  In LS, there is a psoriasiform lichenoid pattern with deep infiltrates of lymphocytes along the adnexae, especially around the eccrine glands.

 Morphometry

Morphometric analysis of histological features can give a quantitative dimension to histopathology. The results of morphometry parameters such as length of rete pegs, the length of dermal papillae and the ratio of length/average width of rete pegs  can help in achieving the accurate diagnoses of psoriasis and psoriasiform dermatitis. In one study using eye-piece micrometer with the light microscope without special software and found statistically significant results in differentiating psoriasis from psoriasiform dermatitis. The mean length of rete pegs was 1.74 times greater in psoriasis when compared to psoriasiform dermatitis. The ratio of average length and width of rete pegs was considered representative of shape of rete pegs. The higher ratio of length over average width of rete pegs confirms the histopathological finding of slender long rete pegs, which favors the diagnosis of psoriasis.

The dermal vascular changes have been evaluated in different studies by electron microscopy and shown to be due to change from arterial-type vessels to venules. The vascular changes may also precede the epidermal alterations, as shown in some studies. Morphometric parameters of papillary dermal vessels in psoriasis and to compare these with psoriasiform lesions can also be used. Morphometric evaluation of dermal vasculature in psoriasis has shown increased endothelial and luminal volume of vessels compared to control subjects. On light microscopic evaluation of CD34 immunostained sections, biopsies from psoriasis showed much greater microvascular staining in the papillary dermis in comparison to psoriasiform dermatitis.20

 Role of Immunohistochemistry

  Ki-67 and Cyclin D1 Immunostaining

As Psoriasis is a hyperproliferative skin disorder with increased epidermal turnover rate and mitotic index,  proliferation markers Ki-67 (Figure 4) and Cyclin D1 immunostaining  can be used to differentiate psoriasis from non-psoraisis psoriasiform dermatitis( NPPD ) (Figure 5). In a study Ki-67 and Cyclin D1 positive cells were counted per mm2 of suprabasal and total epidermal area by Sezer. et al. 4

Psoriatic lesions have been shown to reveal a higher Ki-67 index compared with normal appearing, non-lesional skin.  In psoriasis group, suprabasal Ki-67 positive cells were more than 75% of the total epidermal Ki-67 positive cells in the epidermis (including basal and suprabasal cell population) in psoriasis group, whereas this ratio was lower than 75% (cut-off value) in NPPD group. The suprabasal/total epidermal count ratio for Cyclin D1 immunostaining was higher in the psoriasis group compared with the NPPD group, but a cut-off value to distinguish between these two was not detected, suggesting that Ki-67 is a more sensitive marker than Cyclin D1 in terms of the presence of a cut-off value and could be a useful tool for dermatopathologists to differentiate psoriasis from other psoriasiform dermatitis.4

 pRb and p53 Immunostaining

Expression levels of pRb and p53 were found to be higher in the psoriasis group  in a study,  compared with the normal epidermis.  The phosphorylation of pRb is associated with cyclin D1, cyclin E and P16.  pRb phosphorylation in psoriasis is incresed by the activity of cyclin D1 and Cyclin E and showed a higher expression of pRb than that of normal epidermal expressions.  Total basal layer cell counts for p53 expression were found to be significantly higher in psorisis group compared with the normal group.5 It is postulated that increased expression of p53 in psoriatic skin is a physiological reaction indicating the attempt  to counteract the proliferation and to repair DNA errors, and is most often expressed as an increased number of mitoses.22

 CD4+ and CD8+ cell distribution

Psoriasis also known as a skin disorder with immunological factors playing an important role in its pathogenesis, and lymphocytic infiltrates, mainly CD4+ and CD8+ cells provide a major contribution in the initiation and maintenance of the lesion. Psoriasis is an autoimmune skin disease characterized by T-cell mediated hyperproliferation of keratinocytes. It is regarded as a T-cell mediated disorder, mainly CD4+ (helper/inducer) lymphocytes along with CD8+ (suppressor/cytotoxic) subsets are known to be associated. T-lymphocytes in psoriatic lesion are in an activated state with expression of HLA-DR and IL-2 receptor. Mixtures of CD4+ T-cells and CD 8+ T-cells are present in papillary dermis and epidermis of psoriatic lesion. T-cell also plays a role in the pathogenesis of psoriasiform lesions, and reported a high proportion of CD4+ T-cells in the dermis on immunohistochemical analysis.6

A comparative study was done by Rana. et al to see the infiltration of CD4+ and CD8+  cells in psoriasis and psoriasiform lesions. The inflammation in the epidermis was present in about half of psoriasis cases and predominant cells were polymorphs. In the upper dermis, inflammation was evident in all cases with predominant cells were lymphocytes. Inflammation in the lower (reticular) dermis was present with mostly lymphocytes.

In psoriasiform lesions the inflammation was present in the epidermis in only few cases showing mixtures of polymorphs and lymphocytes. Within the upper dermis, all cases showed inflammation with predominant of lymphocytes. Few cases showed inflammation in the lower dermis with lymphocytes as majority of the cells. Immunohistochemical staining was done to see the distribution of CD4+ and CD8+ cells.  the distribution of CD4 positive cells was seen in psoriasis patients.  In the epidermis of psoriasis cases only one fifth were positive for CD4+ cells. In the upper dermis, CD4+ cells were present in 92% cases.  In the lower dermis about half of cases were positive for CD4+ cells.

D 8+ positive cells on the other hand were seen in the epidermis in 40% cases.  In the upper dermis, all the cases showed CD8+ positive cells.  In the lower dermis, CD8+ positive cells were found in large number of cases.

An immunophenotyping of the inflammation of psoriasiform lesions showing, CD4+ cells as predominant cells in the upper dermis. In lower dermis area showed 16% cases having CD4+ cells.

Various studies have shown that CD4+ cells are less frequent in psoriatic epidermis. In epidermis CD8+ cells were seen in 40% cases, and 8% in psoriasiform lesions. The difference was statistically significant.  In the upper dermis, one study has shown the mixtures of CD4+ and CD8+ T-cells in psoriasis, whereas psoriasiform group showed that CD4+ cells in abundance.

The difference in amount and pattern of CD4+ and CD8+ T-cells in the various compartments is helpful in differentiating between psoriasis and psoriasiform lesions especially in cases with borderline morphology.6

 Conclusion

Psoriasis, the prototype of psoriasiform dermatitis, is a genetically determined, inflammatory, and proliferative disease of the skin characterized by dull red, sharply demarcated scaly plaques. The two clinical signs, Auspitzs sign and the Grattage test have been described as pathognomonic of psoriasis when biopsy is not done.  However, these signs are present only in untreated patients. Psoriasis has many different clinical differentials as other psoriasiform lesions. Besides, the same patient can present at different times with a different clinical presentation.  Since satisfactory management of the condition requires both symptomatic and specific therapy, it is essential to reach a definitive diagnosis. The recurrent nature and prognosis of psoriasis differs from that of psoriasiform dermatitis, thus, further highlighting the importance of reaching the correct diagnosis. Clinical features, considered alone, may not be reliable. Histopathology is regarded as a gold standard for the diagnosis of most dermatological conditions including psoriasis and constitutes definite hard evidence, which can be preserved for future review.  Though to give a precise diagnosis one relies on clinical correlation, histopathology is essential as it is possible to assign specific diagnosis in most cases with a logical and systematic histopathological approach.  In selected cases morphometry, Ki-67 & Cyklin D1, pRb and p53 immunostaining of keratinocytes can be added when needed. The pattern of T-cell infiltrate by immunophenotyping can give an additional diagnostic clue.

Acknowledgement

The authors are grateful to Faisal Kabir Taj for his help in preparing the figure 1.

 References

  1. Jayalakshmy PL, Babitha AM, Sankar S, Nandakumar G. Histopathological spectrum of Psoriasiform dermatitis. Journal of Pathology of Nepal 2016; 6(12): 975 -980.
  2. Tirumalae R . PsoriasiformDermatoses: Microscopic Approach,Indian J Dermatol. 2013 58(4): 290–293. doi: 4103/0019-5154.113945.
  3. Shirish S. Chanadanwale, Narayanan K. Panicker, Sushmah P. Kulkarni, Komal R. Shah, Kumar H, Yugal K. Sharma1, Sukanya Pal, Morphometry analysis of psoriasis and psoriasiform dermatitis: A retrospective study of 50 cases.  Medical Journal of  D.Y. Patil University 2015; 8(1): 43-47.
  4. Sezer E, Böer-Auer A, Cetin E, Tokat F, Durmaz E, Sahin S and Ince U. Diagnostic utility of Ki-67 and Cyclin D1 immunostaining in differentiation of psoriasis vs. other psoriasiform dermatitis. Dermatol Pract Concept. 2015;5(3): 7-13. 2015;5(3):2ul; 5(3):doi: 5826/dpc.0503a02.
  5. Kim SA, Ryu Y W, Kown J I, Choe M S, Jung J W, Cho J W. Differential expression of cyclin D1, Ki‑67, pRb, and p53 in psoriatic skin lesions and normal skin. MolecularMedicine  Reports 2018;17: 735-742,   DOI: 10.3892/mmr.2017.8015.
  6. Rana S, Zeeba J S, Sujata J, Madhur K: A comparative study of psoriasis and psoriasiform lesion on basis of CD4 and CD8 cell infiltration. Our Dermatol Online. 2012; 3(4): 292-297.
  7. Cowden A., Van Voorhees A.S. (2008) Introduction: History of psoriasis and psoriasis therapy. In: Weinberg J.M. (eds) Treatment of Psoriasis. Milestones in Drug Therapy. Birkhäuser Basel, pp 1-2. DOIhttps: doi.org/10.1007/978-3-7643-7724-3_1.
  8. Langley R G B, Krueger G G, Griffiths C E M, Psoriasis: Epidemiology, Clinical Features, and Quality of Life. Ann Rheum Dis. 2005;64(Suppl II):ii18 23.doi: 10.1136/ard.2004.033217.
  9. Grace W. Kimmel and Mark Lebwohl. Psoriasis: Overview and Diagnosis.Bhutani T et al. (eds.), Evidence-Based Psoriasis, Upsoriasiformdermatitisates in Clinical Dermatology, https://doi.org/10.1007/978-3-319-90107-7_1.
  10. Khan ZA, Malik LM,  Jahangir M,  Prevalence of smoking, alcohol, and comorbid conditions in psoriasis. Journal of Pakistan Association of Dermatologists 2010; 20:212-216.
  11. Sako E, Famenini S, Jashin J Wu.  Trends in Type of Original Psoriasis Publications by Decade, 1960 to 2010.   Perm J 2016 Fall;20(4):15-060. http://dx.doi.org/10.7812/TPP/15-060.
  12. Armstrong AW, Harskamp CT, Armstrong EJ. The association between psoriasis and obesity: a systematic review and meta-analysis of observational studies. Nutrition and Diabetes (2012) 2, e54; doi:10.1038/nutd.2012.26..
  13. Samuel T. Hwang, Nijsten T and Elder J T. Recent Highlights in Psoriasis ResearchJournal of Investigative Dermatology 2017; 137(3):550 -556; doi:10.1016/j.jid.2016.11.007.
  14. Busse K, Liao W.Which Psoriasis Patients Develop Psoriatic Arthritis? Psoriasis Forum. 2010; 16(4): 17–25.
  15. Ayala-Fontánez N,  Soler D C, McCormick TS.   Current Knowledge on Psoriasis and Autoimmune Diseases.    Psoriasis: Targets and Therapy 2016;6: 7–32;.org/10.2147/PTT.S64950.
  16. Benhadou F, Mintoff D, Schnebert B, Thio H B. Psoriasis and Microbiota: A Systematic Review. Diseases 2018, 6, 47; doi:10.3390/diseases6020047.
  17. Capon F. The Genetic Basis of Psoriasis. Int J Mol Sci. 2017;18(12):2526. Published 2017 Nov 25. doi:10.3390/ijms18122526.
  18. Mobini N, Toussaint S, Kamino H: Noninfectious Erythematous, Papular, and Squamous diseases. In Lever’s Histopathology of the Skin, 10 th Edition. Edited by Elder DE, Elenitsas R, Johnson BL, Murphy GF, Xu X.  India, Woltrs Kluwer, 2009, pp 169-203.
  19. Flatz L, Conrad C. T-cell-mediated inflammation in psoriasis: pathogenesis and targeted therapy.Psoriasis: Targets and Therapy 2013; 3:1-10. org/10.2147/PTT.S26339.
  20. GuptaS,  KaurM,  Gupta R, SinghS, PantL, SinghP P.Dermal Vasculture in Psoriasis and Psoriasiform dermatitis: a  Morphometric study. Indian J Dermatol. 2011 Nov-Dec; 56(6): 647–649. doi: 10.4103/0019-5154.91820: 10.4103/0019-5154.91820
  21. Mehta S, Singal A, Bhattacharya SN. A  study of clinicohistopathological correlation in patients of  psoriasis and psoriasiform dermatitis. Indian J Dermatol Venereol Leprol 2009;75:100.
  22. Baran W, Szepietowski J. C, Szybejko-Machaj G. Expression of p53 protein in psoriasis. Acta Dermatoven APA 2005;14(3):79-83.

jhc-2019-jul-v-3-n-2-histopathological-huq-n

Histopathological Pattern of Central Nervous System Infection: Experience of 61 cases at Referral Neuroscience Hospital in Bangladesh

 Huq N,1 Haque ME,2 Jahan N,3 Yusuf MA,4 Baqui MN,5 Rozhana S,6 Shirin S,7 Islam MN8

Abstract

Background: Central nervous system (CNS) infections presenting as space occupying lesions are not uncommon in a developing country like Bangladesh.
Objective: The purpose of the present study was to see the histomorphological pattern of CNS infections.
Methodology: This retrospective study was carried out in the Department of Neuropathology at National Institute of Neurosciences & Hospital (NINS&H), Dhaka, Bangladesh during the time period of June 2013 to March 2018 for a period of around five (05) years. All the patients biopsied in neurosurgical department and was reported as infectious lesions from the Department of Neuropathology of NINS&H were selected as study population.
Result: A total number of 2504 cases of surgical specimens were reported during the study period of which 61(2.4%) cases were infectious lesions. Among 61 infectious cases tubercular lesion, suppurative and fungal causes of infection were found in 33(54.1%) cases, 21(34.4%) cases and 7(11.5%) cases respectively. Majority of the study population was in less than 40 years of age group which was 48(80.0%) cases. Male was predominant than female which was 38(62.3%) cases and 23(37.7%) cases respectively.
Conclusion: In conclusion tubercular infection is the most common CNS infection followed by suppurative and fungal infection.

[Journal of Histopathology and Cytopathology, 2019 Jul; 3 (2):143-150]

Key words: CNS infection, Tuberculosis, Fungal infection

  1. *Dr. Naila Huq, Associate Professor, Department of Neuropathology, National Institute of Neurosciences & Hospital, Dhaka, Bangladesh. nailahuqpopy@gmail.com
  2. Mohammad Enamul Haque, Senior Consultant, Victoria Hospital, Narayanganj, Bangladesh. doctorenamk43@gmail.com
  3. Nasreen Jahan, Research assistant, National Institute of Neurosciences & Hospital, Dhaka, Bangladesh.dr.nasreen2014@gmail.com
  4. Md. Abdullah Yusuf, Assistant Professor, Department of Microbiology, National Institute of Neurosciences & Hospital, Dhaka, Bangladesh. ayusuf75@yahoo.com
  5. Nazmul Baqui, Senior Lecturer, Unit of Pathology, Faculty of Medicine, AIMST University, Kedah, Malaysia. doctornazmul@yahoo.com
  6. Sharmin Rozhana, Lecturer, Unit of Microbiology, Faculty of Medicine, AIMST University, Kedah, Malaysia. srozhana@gmail.com
  7. Sadia Shirin, Medical Officer, Department of Neuropathology, National Institute of Neurosciences & Hospital, Dhaka, Bangladesh. sadiashirin77@gmail.com
  8. Md. Nowfel Islam, Professor & Head, Department of Pathology, National Institute of Neurosciences & Hospital, Dhaka, Bangladesh. nowfel2008@gmail.com

 *For correspondence

 Introduction

Top of FormBottom of FormDiseases causing multiple ring enhancing lesions of the brain are infectious, neoplastic, inflammatory or vascular origin.1-3 Central nervous system (CNS) infections are important because of many emerging and reemerging pathogens. Now a day’s persons are at increased risk of CNS infection due to acquired immunodeficiency syndrome (AIDS). CNS becomes a watershed for Human Immunodeficiency Virus (HIV) infection.4 Infections are also common among the recipients of organ transplantation.2-5 Infections are caused by a wide variety of organisms including bacteria, fungi, parasite and virus. Environmental factors in tropical countries play a significant role in the pathogenesis of CNS fungal infections. Immunocompromised patients are commonly susceptible to fungal infection.5 But exposure to drug or contaminated devices can also cause CNS fungal infection in immunocompetent person. Even People of endemic region can get CNS infection following heavy exposure to fungi.4, 6

Radiology is not always helpful for the diagnosis of CNS infection. Some treatable infectious diseases can even mimic the MRI features of demyelinating disease like multiple sclerosis.3,7,5 Although neoplasms are the common considerations in the presence of enhancing lesions with perilesional edema and mass effect on neuroimaging; non-neoplastic conditions particularly, infectious lesions can have similar imaging characteristics.1

Histopathological diagnosis is essential in case of neoplasm for diagnosis, grading as well as treatment. But infectious lesions that could not be diagnosed by noninvasive procedure also need biopsy. Distinguishing non-neoplastic from neoplastic lesion is extremely important to relieve the patient from the potential side effect of chemotherapy and radiotherapy.3 On the other hand, though brain infections are rare but due to limited space and involvement of vital areas they are associated with high morbidity and mortality.2,8

As Bangladesh has conservative society; HIV infection is not so common. However, like other part of the world, Bangladesh deals with a considerable number of patients having organ transplantation. Moreover, it is one of the densely populated countries of the world. Communicable diseases impose heavy burden on health care system. Tuberculosis is an emerging global health problem. In a country with huge population burden, poor hygiene, malnutrition, less health awareness of people, tuberculosis as well as other infections with involvement of CNS is not rare. There are a very few study regarding the frequency or prevalence of CNS infection in Bangladesh. This study was focused on the frequency and distribution pattern of CNS infections in Bangladesh.

 Methods

The present retrospective study was based on the data collected from the Department of Neuropathology NINS&H, Dhaka, Bangladesh during the time period of June 2013 to March 2018 for a period of around five (05) years. In this study the data of the patients who were underwent CNS surgery and histopathologically diagnosed as infectious lesions were collected. Cases of meningitis were not included in this study as diagnosis of meningitis based only on CSF examination. All extra-cranial skin, soft tissue and bony infectious lesions were excluded from this study. Specimens were stained by routine Hematoxyline & Eosin (H&E) stain. Furthermore, Zeihl-Neelsen stain was performed in all cases of tuberculosis. Periodic Acid Schiff (PAS) stain was done in all cases of fungal infection. Statistical analyses were performed by Statistical Package for Social Science (SPSS) software, versions 22.0 (IBM SPSS Statistics for Windows, Version 22.0. Armonk, NY: IBM Corp.). Continuous data that were normally distributed were summarized in terms of the mean, standard deviation and minimum, maximum. Categorical or discrete data were summarized in terms of frequency and percentages.

 Result

A total number of 2504 cases of surgical CNS specimens were reported during the study period of which 61(2.4%) cases were infectious lesions. Only cases of infectious lesions were further analyzed. The age range of patients was 9 months to 85 years. The patients were stratified into 4 groups which were less than 20 years, 20 to 40 years, 40 to 60 years and more than 60 years. Most of the patients belong to 20 to 40 years age group which was 26(42.6%) cases followed by less than 20 years which was 23(37.7%) cases. CNS infection was very rare in more than 60 years of age; only two cases were found in this age group. However, male predominance with a male to female ratio of 1.7:1 was seen. Male was 38(62.3%) cases and female 23(37.7%) cases respectively (Table I).

In 61.0% cases of histologically diagnosed CNS infections radiological diagnosis were tumors. However in 39.0% cases radiological diagnosis was infection which correlates with the histological diagnosis. In 19 cases radiological diagnosis correlates with the histopathological diagnosis and all of them were tubercular lesion. Radiological diagnosis did not correlate with histopathological diagnosis in 32 cases. And radiology was not available in 10 cases.


Of the total 61 cases 33(54.1%) cases were tubercular, 21(34.4%) cases were suppurative and 7(11.5%) cases were fungal infection. AFB stain done in 30 cases of tuberculosis and result was negative. All cases of fungal infection were further stained by PAS stain and found positive.

 Discussion

CNS includes a wide variety of diseases ranging from suppurative, tubercular, fungal, parasitic and viral infection. For the diagnosis of these cases combined approach of clinical, radiological, CSF and histopathological examination are necessary. There is a scarcity of research works related to the pattern of CNS infections in Bangladesh. As National Institute of Neurosciences & Hospital (NINS&H) is a tertiary level referral hospital in Bangladesh, it deals with different neurological diseases having a well-developed neurosurgery department. Therefore, a great number of patients attend in this hospital.

CNS infection producing space occupying lesions are not uncommon in Bangladesh. About 2.4% of surgical specimens of this study belong to infectious lesions. The age range of the study population was 9 months to 85 years with highest percentage 42.6% cases between 2nd to 4th decades, followed by 37.7% cases in less than 20 years. CNS infection was very rare in more than 60 years of age; only two cases found in this group. The age distribution is consistent with most of the previous studies conducted in different parts of India.9,10,11 In our study 62.3% cases were male and the male to female ratio was 1.7:1. A male predominance seen in most of the reported studies indicating that male are more prone to these infections.9,10,11 This may be due to more exposure of the male of this age group to the environmental agents, vectors due to their outward activities.9 Some zoonotic infections like Neurobrucellosis occur due to occupational exposure.12 Moreover, in the developing countries male got priority over the female in getting treatment facilities.9 This observation matches with Bangladesh having the similar socioeconomic pattern.

We analyzed the anatomical location of the total 61 cases. It has been observed that most of the cases 49(80.0%) were cranial and 12(20.0%) cases were in spinal location. The percentage could be different if lesion like Pott’s disease would include in the study. Rosenblum5 has reported that 20.0% of brain abscess are not associated with predisposing bacterial infection; however, remaining results are from established pyogenic infection in extraneural site. Contiguous spread of infection can result from sinusitis, otitis, dental sepsis and pyogenic infection of face and scalp which causes intracerebral abscess or subdural empyema.5 Contamination of the CNS can occur in three routes. Arterial route is the main route of contamination and the disposition of intracerebral arterial division causes development of diseases in this way at the junction of white matter and gray matter or in the territory of perforating artery. Therefore, frontal or temporal region lesion is most common. Spinal anomalies predispose to intramedullary abscess but such infections are extremely rare5. Herpes simplex, Rabies, Varicella Zoster or a few viruses disseminated through neural route. Direct contamination can result from cranial or vertebral wound or following intracranial surgery. All these explanations suggest that cranial location is more common site of CNS infection particularly in case of acute bacterial infection which is similar to our study.5,8 Another study has been mentioned that infectious lesions in the brain stem are very rare.13

Among 61 cases radiology is not available in 10 cases which are histologically diagnosed as CNS infection. In the remaining, radiological diagnosis correlates with the histopathological diagnosis in 39.0% cases. However, in 61.0% cases radiological diagnosis are tumors. From biostatistical point of view it is not the indicator of sensitivity of radiology. As cases of CNS tumors were not included in the study, it would be a biased statement.

In radiology, neoplasm is the common consideration in enhancing lesions with perilesional edema and mass effect. But infectious lesion, occasionally demyelinating disease can share the similar imaging characteristic1,5. There are some limitations of early imaging and overlapping imaging appearance of many of the infections. Pyogenic abscess often show amino acid at spectroscopy.  Neurotuberculosis, neurosyphilis shows nodular meningeal enhancement with or without vasculitis which can also be seen in fungal infection. Some diseases like, neuro-cysticercosis, echinococcosis may have highly characteristic imaging pattern. But many other infections share common imaging findings. So, a high degree of suspicion is required to assume the diagnosis of CNS infection in radiology.1,14

Of the total 61 cases 54.1% cases are tubercular; 34.4% cases are suppurative and 11.5% fungal. As primary tuberculosis has high prevalence in Bangladesh, CNS tuberculosis might be the commonest presentation in this study. Garg RK3 et al also mentioned intracranial tuberculoma as frequently encountered brain lesion in tropical country. Bacteria are responsible for majority of suppurative infections of CNS and its covering.5 According to working criteria, cases of meningitis are not included in this study. Pyogenic abscess is the second common presentation (34.4% ). Our study is limited by non-availability of relevant microbiological analysis. So type of organism producing pyogenic abscess could not be determined from this study.

We found 7 cases of fungal infection. One of them was suffering from rheumatoid arthritis and receiving treatment with methotrexate. And another was a baby of 9 monthsage. Rest of the patients has no known history of immunodeficiency. Incase of fungal infection we found highest incidence of aspergillosis(4) followed by zygomycosis(2). Only one case of phaeohyphomycosis was found. A hospital based study of India also shows increased incidence of hyphal form like aspergillosis and Zygomycosis in non immunocompromised host.15The cryptococcus usually causes meningitis and rarely presentas cryptococcoma.16,17 Therefore, the cryptococcus is not found in this study.

CNS parasitoses include a great variety of protozoa and helminth.5,17 We did not find any case of neurocysticercosis, toxoplasmosis, echinococcosis, malaria, schistosomiasis and also rare amoebic infection of CNS. A study in India by Bhalla et al9 showed that these infections produce intracranial mass lesion in HIV positive patients. An HIV infected patient having CD4 cell count less than 200 cells/µL is at high risk for opportunistic brain infection. HIV infection is not so common in Bangladesh in comparison with other South Asian country like India or Thailand. As patients of HIV get treatment only in Infectious Disease Hospital (IDH) of Bangladesh, the data of those patients could not be included in this study. These infections may be less frequent in our environment or poor access of our people to the tertiary level hospital like NINS&H may result such outcome. As most of the affected people belong to lower socioeconomic condition the people may die before reaching the health care system. Another study in India showed that some of these infections of nervous system diagnosed mostly in autopsy specimen.5,18 A study in Hill tracts of Bangladesh; endemic for malaria showed significant cases of cerebral malaria in autopsy specimens.19 As facilities of autopsy are not available in our institute the study might be missing these infections.


Conclusion

Tubercular infection is the most common CNS infection followed by suppurative and fungal infection in biopsied specimen. Less than 40 years age group is the most vulnerable age group. High clinical suspicion, awareness of imaging pattern and microbiological approach can minimize the need for brain biopsy. Further large scale multi-institutional study including autopsy should be carried out.

 References

  1. Santosh V, Mahadevan A, Chickabasaviah YT, Bharath RD, Krishna SS. Infectious lesions mimicking central nervous system neoplasm. Semin diagn pathol, 2010;27(2):122-35
  2. Sundaram C, Shankar SK, Thong WK, and Villamizar CAP. Pathology and diagnosis of Central nervous system infections. Pathology Research International, 2011, Article ID878263:1-4
  3. Garg R K, Singha M K, Multiple ring-enhancing lesion of the brain. Journal of Postgraduate Medicine 2010;56(4):307-316
  4. Wig N, Wali JP. Central nervous system and HIV/AIDS. Journal of Indian Academy of Clinical Medicine Vol. 2008;5(2):164-168
  5. Rosenblum MK. Central nervous system in Rosai and Ackermans Surgical Pathology.10th vol.2,2327-2338
  6. Rodriguez T. Fungal infection of the CNS: Diagnostic and Treatment Approaches. Neurology adviser, 2018 May, 1-8; Website: https://www.neurologyadvisor.com/topics/general-neurology/fungal-infections-of-the-cns-diagnostic-and-treatment-approaches/
  7. Rocha AJD, Littig IA, Nunes RH, Tilbery CP. Central nervous system infectious diseases mimicking multiple sclerosis: recognizing distinguishable features using MRI. Arq Neuropsiquiatr 2013;71(9-B):738-746
  8. Sarrazin J-L, Bonneville F, Blondel GM. Brain infections in Diagnostic and Interventional Imaging 2012;93:473-490
  9. Bhalla A, Kharbanda PS. Tropical CNS infections: one must not forget. Update on Tropical Fever 2011;75-86
  10. Joshi R, Clinical presentation, etiology and survival in adult acute encephalitis syndrome in rural Central India in Clin Neurol Neurosurg.2013;115(9):1753-1761
  11. Modi A, Atam V, Jain N, Guth M, Verma R. The etiological diagnosis and outcome in patients of acute febrile encephalopathy: a prospective observational study at tertiary care center. Neurol India 2012;60(2):168-173.
  12. Algahtani H, Shirah B, Abdulghani D, Farhan R, and Algahtani R,Occapational Neurobrucellosis Mimicking a Brain Tumor: A Case Report and Review of the Literature in Case Report in infectious Diseases ;Volume 2017, Article ID 1434051:1-5
  13. Hall WA, Infectious lesions of the brain stem in Neurosurg clin N Am. 1993;4(3): 543-51
  14. Robert Y. Shih LTC, Kelly K. Koellar, MD Bacterial, Fungal and Parasitic Infections of the Central Nervous System: Radiologic-Pathologic correlation and Historical perspectives. Radiographics 2015;35(4)4:1141-1169
  15. Shankar SK, Mahadevan A, Sundaram C, Sarkar C, Chako G, Lanjewar D N, Santosh V, Yasha TC, Radhakrishnan V. Pathobiology of fungal infections of the central nervous system with special reference to the Indian scenario. Neurology India 2007;55(3):198-215
  16. Gupta K, Radotra B. Non-neoplastic Lesions Mimicking CNS Tumors. Essentials of Diagnostic Surgical Neuropathology: 230-239
  17. Matthew P. Frosch, Douglas C. Anthony, Girolami UD, The central nervous system in Robbins and Cotran, Pathologic basis of disease, eighth ed. 1299-1309
  18. Shankar SK, Mahadevan A, Parmar S, Histological Atlas of Common Infections of the Nervous System With Teaching Slides:1-64
  19. Islam SMJ, Uddin MJ, Haque WS, autopsy findings in cerebral malaria, Journal of Armed Forces Medical College  Bangladesh, December 2006; vol 2(2).

jhc-2019-jul-v-3-n-2-The-Role-yasmin-i

The Role of Special Stains in Trephine Biopsy of Lymphoma

 *Yesmin I,1 Begum F,2 Yunus A,3 Kabir AL,4 Baqui MN5

 *Dr. Israt Yesmin, Specialist Pathology, Pathology and Laboratory Medicine, Square Hospital, Dhaka. badhanydr29@gmail.com

  1. Ferdousy Begum, Associate Professor, Department of Pathology, Bangabandhu Sheikh Mujib Medical University, Dhaka. ferdousy_begum2000@yahoo.com
  2. ABM Yunus, Professor & Chairman, Department of Haematology, Bangabandhu Sheikh Mujib Medical University, Dhaka. abmyunus.bsmmu@gmail.com
  3. Amin Lutful Kabir, Associate Professor, DEPT of Haematology, BSMMU Email aminlutful@gmail.com
  4. Muhammad Nazmul Baqui, Senior Lecturer, Faculty of Medicine, AIMST University, Kedah, Malaysia. doctornazmul@yahoo.com

*For correspondence

 Abstract

Background: Accurate diagnosis of lymphoma is always challenging to histopathologists. Aside from routine H& E stain special stains play an important role inreaching the final diagnosing of  lymphomacases. Here we have studied the use of these special stains in trephine biopsy material of lymphoma cases.
Methods: This descriptive cross sectional study was carried out at the Department of Pathology Bangabandhu Sheikh Mujib Medical University (BSMMU), Dhaka, from July 2012 to June 2014. Total 17 cases, which underwent trephine biopsy were included in this study. Different special stains and immunostains were done to reach the final diagnosis. Statistical analyses were performed to find out the usefulness of these special stains.
Results: Fourteenpatients were male and rests were female. Mean age of the patients was 41.8±12.5 years. IHC of trephine biopsy material aids in diagnosis of lymphomatous infiltration with further sub classification. While conventional H&E and giemsa stain revealed only 6(35.3%) cases with lymphomatous infiltration of bone marrow. Among these 14 cases, 10 (58.8%) cases were B-NHL, 3 (17.6%) cases were T-NHL and rest 1(5.9%) was lymphocyte-rich classical Hodgkin lymphoma.
Conclusion: It was found that, use of special stains and IHC of trephine biopsy material of lymphoma cases improved the diagnostic accuracy of lymphoma.

[Journal of Histopathology and Cytopathology, 2019 Jul; 3 (2):134-142]

Key words: Trephine biopsy

Introduction

Trephine biopsy of the bone marrow has wide application in clinical medicine. Its important use is in the evaluation of patients with various haematological disorders like malignant lymphoma, acute leukaemias, myeloproliferative disorders, myelodysplastic syndromes, metastatic tumor, granulomatous disorder, myelofibrosis, aplastic anaemia and plasma cell dyscrasias. Examination of the bone marrow aspirate and trephine biopsy is essential for the diagnosis of bone marrow disorders. The aspirate and trephine biopsy provide complimentary and useful information. It is recommended that both bone marrow aspirate and biopsy be routinely performed for correlation of representative findings.

The bone marrow trephines are particularly useful in identifying focal lesion that may be less apparent on aspirate smear alone. The bone marrow biopsy is also a common and important staging procedure that is performed routinely on patients with hematologic and non-hematologic malignancy. Pathomorphological examination of trephine biopsies of the bone marrow represents a standard method for the diagnosis and staging of hematological neoplasms and other disorders involving the bone marrow.  The use of special stains in bone marrow pathology should be determined following examination of the routinely stained biopsy and the patient’s clinical history.1 Although conventional morphology remains the gold standard for paraffin embedded BM trephines, IHC staining has become an integral part of the diagnostic and prognostic workup.2 Distinction of the most common type of B-NHL in the trephine biopsy can be difficult on morphological ground alone due to overlapping cytological features and distribution pattern and therefore require IHC and occasionally molecular data for primary diagnosis.2

Non Hodgkin lymphoma (NHL) composed of small B lymphocytes comprises the majority of lymphoma infiltrates in the bone marrow. Bone marrow involvement is seen in virtually 100% of B cell chronic lymphocytic leukemia (B-CLL) / small lymphocytic lymphoma (SLL), in almost all cases of lymphoplasmacytic lymphoma (LPL) and hairy cell leukemia (HCL), in 55-93% of mantle cell lymphoma (MCL), in 50-60% of follicular lymphoma (FL) and invariably in splenic marginal zone B cell lymphoma (SMZL). In nodal and extra nodal marginal zone B cell lymphoma the marrow involvement is found in 10-30% cases.2

The pattern of bone marrow involvement is one of the most important hints for diagnosis. Different patterns of bone marrow infiltration by NHLs are recognized, namely paratrabecular, randomly focal / intertrabecular / non paratrabecular, interstitial, diffuse and sinusoidal / intravascular. In some cases, multiple or mixed pattern are present in the same specimen. Although most infiltrates are easily recognizable in standard stains, sparse interstitial and sinusoidal involvement can be practically undetectable by conventional morphology and requires IHC to highlight the neoplastic population.2

Lymphoma demonstrate significant increased incidence rates throughout the world and causes mortality.3 Though uses of special histochemical stain in trephine biopsy is an established practice in histopathology, the application of immunohistochemistry (IHC) to diagnostic bone marrow trephine biopsy specimen is a relatively new practice.4 IHC is a powerful auxiliary technique for the diagnosis of hematologic disorder in bone marrow trephine biopsies.2 IHC reveals clear architectural features and estimates tumor cellularity in paraffin sections. By using IHC an accurate characterization and primary classification of lymphoid neoplasm is possible in the majority of cases and expands the diagnostic scope of bone marrow histology.2 The ability to define such subgroups is increasingly important as treatment is tailored not only to specific types of lymphoma but also on the basis of their prognostic group.5 Therefore the aim of this study was undertaken to see the role of special stains in bone marrow trephine biopsy in the diagnosis of lymphoma and to detect lymphoma of bone marrow and their typing.

Methods

This descriptive cross sectional study was carried out at the Department of Pathology Bangabandhu Sheikh Mujib Medical University (BSMMU), Dhaka, from July 2012 to June 2014. A total of 17 patients of different age and sex were selected from the department of Hematology BSMMU, Dhaka and other different institutes of Dhaka by using non probability sampling method. Patients who underwent trephine biopsy and histologically and clinically suspected as cases of lymphoma and cases accompanied by clinical information were included in this study. Exclusion criteria include patients who were not suspected as cases of lymphoma in histological diagnosis, specimen having severe crush artifact and specimen less than 1 cm in length. According to standard protocol the biopsy samples were taken from the posterior superior iliac spines under local anesthesia. Formalin fixed trephine biopsy sample were allowed to fix over night at room temperature in 10% buffered formalin fixative. Trephine biopsy samples collected from haematology department of BSMMU and other different institutes of Dhaka were decalcified in 10% formic acid for four hours followed by wash in running tap water for an hour.  Routine processing and paraffin embedding were done according to BSMMU standard tissue processing protocol in automated machines.  Paraffin blocks were made.  Subsequent tissue sections were analyzed by using routine H&E stain, periodic acid Schiff (PAS) stain, Giemsa stain and a primary histological diagnosis were made.

Sections with at least five well preserved marrow spaces were studied for cellularity, normal hematological elements, presence of infiltration if any, the extent, histologic pattern and morphology of infiltration and other secondary changes. The morphology and histologic pattern of infiltration were categorized as diffuse, interstitial, focal (non-paratrabecular), paratrabecular and mixed patterns. Diffuse pattern was defined when there was extensive replacement of the marrow elements, both hematopoietic tissue and fat, obscuring the marrow architecture.  Interstitial pattern was indicated when individual neoplastic cells were interspersed between hematopoietic cells and fat, focal, where nodular aggregates were seen separated by normal hematopoietic marrow, paratrabecular, when infiltrate aggregates were seen immediately adjacent to bony trabeculae.

2–3 μm thick sections were cut from the paraffin blocks for IHC. EnVision method was followed. The immunohistochemical staining procedure of all antibodies except TdT was performed in the IHC lab of BSMMU by following its staining protocol. Table I shows the IHC panel done for diagnosis.

Results of immunostains were assessed by light microscopy using a 10× objective lens with subsequent use of 20 and 40 lenses for confirmation. Immunostains results were expressed as positive, weakly positive or negative. Cases where quantification of specific type of immunohistochemical markers positive cells are needed counted at x40 magnification, excluding cortical and trabecular bone, periosteal connective tissue, adipose tissue or areas of haemorrhage. The specific immunohistochemical marker positive cells were counted in five or more randomly selected fields and the number of positive cells was expressed as a percentage of total number of bone marrow nucleated cells.  Slides were reviewed by two senior histopathologists. Subsequently special histochemical stains and immunohistochemical finding was analyzed and final reports were issued. This was performed in the department of pathology of BSMMU, Dhaka.

 Results

Age, sex and clinical findings

It was observed that maximum case (35.3%) patients belonged to age grouped 31-40 years. The mean age was found 41.8±12.5 years with range from 20 to 70 years. Majority14 (82.4%) patients were male and 3(17.6%) were female indicating male predominance. Male and female ratio was 4.7:1. Out of 17 patients of the present study 13 patients had fever, 6 complained of weakness and 6 presented with hemorrhagic manifestation e.g. gum bleeding, cyanosis, bleeding spot etc. The other complains included weight loss, bone and joint pain, swelling of whole body, night sweat, pruritus, yellow discoloration of skin and sclera, neck swelling, oral ulcer etc. Anaemia was the most prevalent (88.2%) feature. Other signs included jaundice, oedema, cyanosis etc. Five (29.4%) patients had generalized lymphadenopathy, two (11.8%) had grouped palpable lymph node, one (5.9%) had bony tenderness and all had normal tonsil.

 Ultrasonographic findings

Among 17 cases USG reposts were not available in 5 cases. Two (11.8%) patients had splenomegaly, 2(11.8%) had hepatomegaly, 6(35.3%) had hepatosplenomegaly, 1(5.9%) had abdominal lymphadenopathy and USG findings were normal in 1(5.9%) cases.

Bone marrow examination

Comparison of Primary histological diagnosis with final diagnosis after IHC

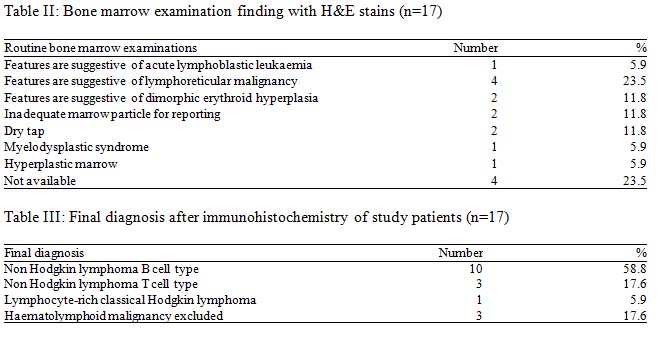
Out of these 17 cases 14 cases as various types of lymphoma. In the present study, primary histological diagnosis on trephine biopsy was made as haematolymphoid malignancy unclassified in 11(57.1%) cases and NHL in 6(42.9%) cases. Fibrosis was not seen in any of the 17 cases.


Trephine biopsy samples of 17 cases were histologically analyzed with the help of H&E stain along with PAS and Giemsa stain. Five patients were finally diagnosed as NHL by primary histological diagnosis was made on the basis of different pattern of abnormal cellular infiltration in the bone marrow trephine biopsy.

Discussion

In this series it was observed that most of the patients with haematological disorder were in 4th decade and their mean age was 36.1±15.01 years. Male to female ratio was almost 3:1. Similarly study conducted by Chen et al. (2000) observed male to female ratio was 2.9:1.6 Similar observations regarding the male predominant were also made by Matsuo et al. (2003) and Lone & Naeem (2011).7 On the other hand Kumar et al. (2009) observed female predominant, where they found female to male ratio was almost 5:1.8

 The pattern of marrow involvement also differs to some extent in various NHL subtypes, for example paratrabecular infiltration is strongly associated with follicular lymphoma. A bone marrow biopsy performed in patients with low grade lymphoma sometime shows unexpected high grade transformation, which necessitates a different therapeutic approach.9

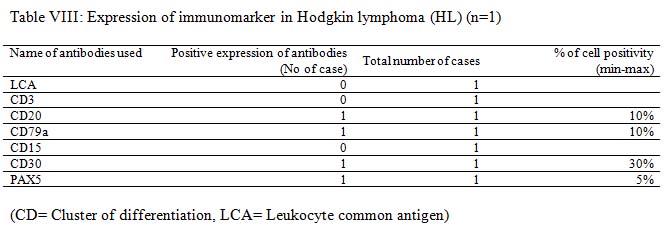
 Among initial 11 cases of haematolymphoid malignancy unclassified in trephine biopsy were finally seven of them were diagnosed as B-NHL and one case as Hodgkin lymphoma. The remaining three cases were finally excluded from haematolymphoid malignancy. This result indicates the importance of IHC in the diagnosis of haematolymphoid malignancy. The remaining six cases of NHL were further sub classified as B-NHL and T-NHL (Table IV).

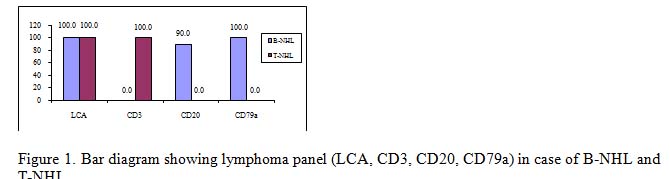
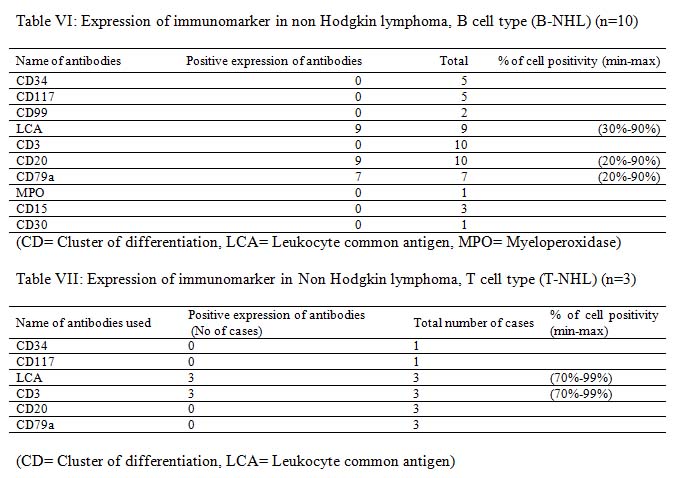
It is very much clear that trephine biopsy reports are superior as it could specify the diagnosis in most of the cases with the exception of cases of B-NHL and T-NHL. The latter cases were diagnosed only on the basis of CD3, CD20 and CD79a immunomarker. The incidence of bone marrow involvement in extra nodal MZL is lower (~20%) than in other low grade B-NHL, albeit recent studies described BM infiltration in up to 44% of cases.10

West et al. (2002) studied 61 cases (26 follicular lymphoma and 35 benign or atypical aggregates). They found that no single stain is sufficient for identification of neoplastic lymphoid aggregates. However, this distinction was made possible by using a panel of antibodies. The most useful antibodies were CD10, bcl-2, CD5, and CD20. Most benign or atypical aggregates do not express CD10 and CD23.11

Bone marrow specimens from 317 patients with non-Hodgkin’s lymphoma (NHL) obtained at initial staging was evaluated for the presence of lymphoma or benign lymphoid aggregates were studied by Conlan et al. (1990). They have found thirty-two percent (102 patients) had lymphoma in their bone marrow, and 9% had benign lymphoid aggregates. Bone marrow lymphoma was present in 39% of low-grade, 36% of intermediate-grade, and 18% of high-grade lymphomas. The bone marrow was involved in 25% of patients with diffuse large-cell or immunoblastic NHL. Bone marrow involvement did not affect survival of patients with low-grade NHL, but survival was significantly shorter (P<0.05) for patients with intermediate- and high-grade NHL with bone marrow involvement. Bone marrow involvement was equally common in B-cell and T-cell NHL (31% v 32%).12

Bone marrow involvement by lymphoma is considered a systemic dissemination of the disease arising elsewhere, although some tumors may arise primarily in the bone marrow microenvironment 13. IHC is important for lymphoma in particular those with heterogeneous histology to establish accurate diagnosis and adequate therapy14.

Bone marrow aspiration and bone marrow biopsy are important diagnostic procedures for diagnosis of hematological, non-hematological malignancies and other diseases. These procedures are also valuable for follow up of patients undergoing chemotherapy, bone marrow transplantation and other forms of medical treatment. In the study conducted by Toi et al. (2010),  comparative evaluation of all such bone marrow aspiration (BMA) and bone marrow biopst (BMB), to see the complementary role of both the procedures, to study the advantages and disadvantages of both the procedures done simultaneously. There was 61.25% positive correlation between BMA and BMB in the study15.

Conclusion

It can be concluded that correct diagnosis can be made in majority of cases with the application of PAS, Giemsa and limited number of immunomarker. Correct and relevant clinical information along with appropriate special stain of bone marrow trephine biopsy improves the diagnostic accuracy of lymphoma cases.

 References

  1. Brunning RD, Arber DA, 2011. Bone marrow. In J, Rosai Rosai and Ackerman’s Surgical Pathology, Tenth edition, Mosby Elsevier Inc, pp. 1927-2012.
  2. Kremer M, Quintanilla-Martínez L, Nährig J, von Schilling C, Fend F. Immunohistochemistry in bone marrow pathology: a useful adjunct for morphologic diagnosis. Virchows Arch Int J Pathol. 2005 Dec;447(6):920–37.
  3. Tahmasby B, Marnani AB, Maleki M, Barouni M, Mousavi SH, Naseriyan B, et al. Blood malignancies in Mazandaran province of Iran. Asian Pac J Cancer Prev APJCP. 2013;14(2):1053–6.
  4. Olsen RJ, Chang C-C, Herrick JL, Zu Y, Ehsan A. Acute leukemia immunohistochemistry: a systematic diagnostic approach. Arch Pathol Lab Med. 2008 Mar;132(3):462–75.
  5. Guidelines on the management of acute myeloid leukaemia in adults – – 2006 – British Journal of Haematology – Wiley Online Library [Internet]. [cited 2019 Sep 30]. Available from: https://onlinelibrary.wiley.com/doi/full/10.1111/j.1365-2141.2006.06314.x
  6. Clinicopathological studies on bone marrow involvement of non-Hodgkin’s lymphoma [Internet]. ResearchGate. [cited 2019 Sep 30]. Available from: https://www.researchgate.net/publication/12095478_Clinicopathological_studies_on_bone_marrow_involvement_of_non-Hodgkin’s_lymphoma
  7. Matsuo T, Kuriyama K, Miyazaki Y, Yoshida S, Tomonaga M, Emi N, et al. The percentage of myeloperoxidase-positive blast cells is a strong independent prognostic factor in acute myeloid leukemia, even in the patients with normal karyotype. Leukemia. 2003 Aug;17(8):1538–43.
  8. Kumar S, Rau AR, Naik R, Kini H, Mathai AM, Pai MR, et al. Bone marrow biopsy in non-Hodgkin lymphoma: a morphological study. Indian J Pathol Microbiol. 2009 Sep;52(3):332–8.
  9. Juneja SK, Wolf MM, Cooper IA. Value of bilateral bone marrow biopsy specimens in non-Hodgkin’s lymphoma. J Clin Pathol. 1990 Aug;43(8):630–2.
  10. Feugier P, De March AK, Lesesve JF, Monhoven N, Dorvaux V, Braun F, et al. Intravascular bone marrow accumulation in persistent polyclonal lymphocytosis: a misleading feature for B-cell neoplasm. Mod Pathol Off J U S Can Acad Pathol Inc. 2004 Sep;17(9):1087–96.
  11. West RB, Warnke RA, Natkunam Y. The usefulness of immunohistochemistry in the diagnosis of follicular lymphoma in bone marrow biopsy specimens. Am J Clin Pathol. 2002 Apr;117(4):636–43.
  12. Conlan MG, Bast M, Armitage JO, Weisenburger DD. Bone marrow involvement by non-Hodgkin’s lymphoma: the clinical significance of morphologic discordance between the lymph node and bone marrow. Nebraska Lymphoma Study Group. J Clin Oncol Off J Am Soc Clin Oncol. 1990 Jul;8(7):1163–72.
  13. Primary bone marrow lymphoma: an uncommon extranodal presentation of aggressive non-hodgkin lymphomas. – PubMed – NCBI [Internet]. [cited 2019 Sep 30]. Available from: https://www.ncbi.nlm.nih.gov/pubmed/22251943
  14. Bone marrow aspiration before bone marrow core biopsy using the same bone marrow biopsy needle: a good or bad practice? [Internet]. [cited 2019 Sep 30]. Available from: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC1860622/
  15. Toi PC, Varghese RG, Rai R. Comparative evaluation of simultaneous bone marrow aspiration and bone marrow biopsy: an institutional experience. Indian J Hematol Blood Transfus Off J Indian Soc Hematol Blood Transfus. 2010 Jun;26(2):41–4.